


For a small practice, “services” means people and process working inside your existing practice management system. You keep your software, your payer contracts, your patient relationships and the final say on any write-off. We take over eligibility checks, coding review, claim submission, payment posting, denials, A/R follow-up, patient statements and the monthly report, and we report to you on how the cycle is performing.
The work matters because denials are routine, not rare: among the ACA marketplace plans sold on HealthCare.gov, the one segment where CMS publishes the figures, insurers denied 20% of in-network claims in 2023 (KFF, January 2025), and consumers appealed fewer than 1% of them. A practice that does not work its denials is leaving that money with the payer.
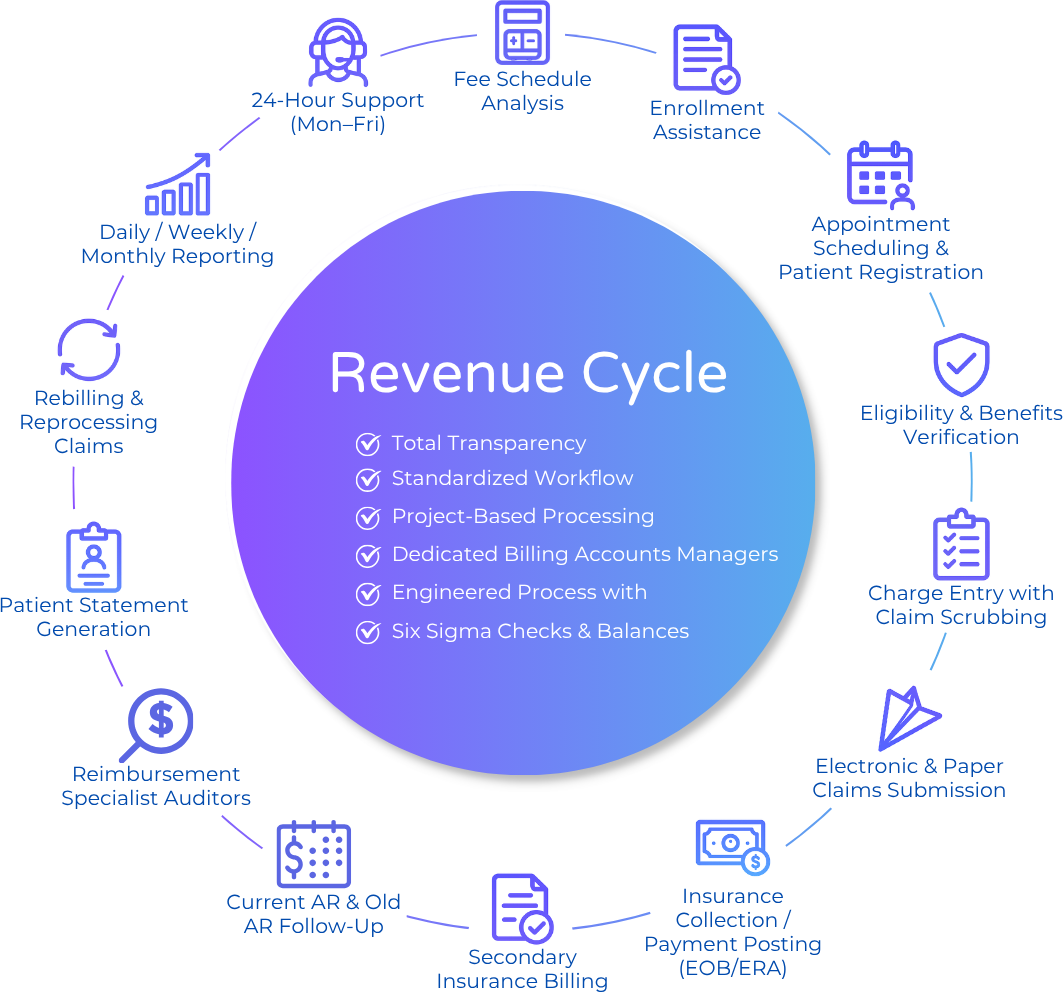
| Number | Stage | What happens | Where it breaks | Our available service |
|---|---|---|---|---|
| 1 | Scheduling & eligibility verification | Before the visit, coverage is confirmed: is the plan active, is the provider in network, what will the patient owe. A verification run the day before the visit catches most of this. | Coverage lapsed, the plan changed, or the deductible was never checked, and the claim is denied weeks later for a reason that was knowable on day one. It is the cheapest stage to fix and the most expensive to skip. | Insurance eligibility verification |
| 2 | Prior authorization | For services that need payer approval, the request is filed and the approval recorded before the service is delivered. The approval number travels with the claim. | The authorization is missing, expired, or does not match the service performed. The payer will not pay, and in most cases the patient cannot be billed for it either. Authorization denials are among the hardest to overturn after the fact. | Prior authorization |
| 3 | Charge capture & medical coding | Every service performed is captured and translated into CPT, ICD-10 and HCPCS codes with the correct modifiers. Coding accuracy is checked before the claim is built, not after it is denied. | Encounters go unbilled, procedures are under-coded, modifiers are missed. Revenue that was earned is never claimed. Under-coding is invisible in a denial report. Nothing is denied. The money simply never arrives. | Medical coding |
| 4 | Claim scrubbing & submission | Claims are checked against each payer's rules, then sent through a clearinghouse inside the payer's filing deadline. Rejections are corrected and resent the same day. | Rejections bounce back from the clearinghouse and sit unnoticed, or a filing deadline passes. A late claim is not a slow claim. It is an unpayable one. Every payer sets its own deadline; some are measured in weeks. | Medical billing |
| 5 | Payment posting | Remittances (electronic ERAs and paper EOBs) are posted against each claim, with contractual adjustments applied correctly. Underpayments, where the payer paid less than the contract allows, are flagged here or never. | Payments are posted late or to the wrong claim, adjustments hide underpayments, and denials buried in the remittance are never surfaced. | Payment posting |
| 6 | Denial management & appeals | Each denied claim is traced to its cause, corrected, and resubmitted or appealed inside the payer's window. A denial that recurs is treated as a process problem, not a claim problem. | Denials are resubmitted without fixing the cause, so they come back. Appeal windows close. The same error repeats next month. | Denial management |
| 7 | A/R follow-up & recovery | Every unpaid claim is worked on a schedule, at 30, 60 and 90 days, until it is paid, corrected, or legitimately closed. Older balances are worked first, because they are closest to being lost. | Balances age past 90 days, get harder to collect with every week, and are written off because nobody had the time. | A/R recovery |
| 8 | Patient statements & balances | After insurance pays, the patient's share is billed clearly and followed up. Statements go out on a fixed cadence with a clear amount due and a way to pay. | Statements go out late or are hard to read, so patients do not pay, and the practice quietly absorbs the balance. | Patient statements |
| Compare | In-house team | Summit Billing Solutions |
|---|---|---|
| Staffing & continuity | One or two people carry all the payer knowledge. A vacation, an illness or a resignation stalls the cycle. | A team, so no single absence stops claims. Continuity is our problem to solve, not yours. |
| Cost structure | Salaries, benefits, software seats and training are fixed costs whether collections are up or down. | A percentage of what is collected, so the cost moves with revenue. You pay more only when you are paid more. |
| Payer expertise | Deep knowledge of your payers, built over years and lost the day that person leaves. | We work the same payers across many practices, so a rule change shows up early and gets fixed once, for everyone. |
| Software & clearinghouse | You choose and manage your practice management system, clearinghouse and vendors. | We work inside your existing system. You keep your software and your data; we do not make you switch. |
| Reporting & visibility | As good as the reports your team has time to build. | A monthly report as part of the service: denials by payer and reason, A/R aging, collections against charges. |
| Control & accountability | Total. You see every claim and can walk over and ask about it. | Less direct control, by design. A named contact and a weekly call are how we keep it from feeling remote. |
We look at your current denial rate, your aging A/R and your top denying payers, and tell you what we find, whether or not you go further with us.
We connect to your existing practice management system and agree the workflow: who does what, how escalations work, what the monthly report covers. Most practices are live within one to two weeks.
Claims go out daily. Remittances are posted as they arrive. Denials are worked to their cause. Aging balances are followed on a schedule. Our RCM services team does this inside your system, so nothing is hidden from you.
You get a report you can read in ten minutes: what was billed, what was collected, what was denied and why, what is aging, and what we changed upstream as a result.


Your claims are worked by a team in the United States, not routed offshore.
You know who is working your account, and you hear from them every week. A familiar face, not a ticket queue.
If we are not earning the relationship, you can leave. That keeps us honest.
We are in Salem, NH, and we bill for practices nationwide, with the state-by-state payer knowledge that takes.
2%
Average claim rejection rate
24 hrs
Claims submitted within
28
Average days in A/R

I’ve been in billing for 30+ years and Summit is the best I’ve worked with. They’re knowledgeable, detailed, and persistent to get claims paid instead of writing them off. They take the burden off providers so we can focus on patients.

We billed in-house for decades, but it was time for a change. I couldn’t be happier with Summit. The transition was seamless thanks to their strong systems and clear communication. If you’re considering a switch, talk to Summit.


Most revenue cycle management services are priced one of two ways: a percentage of what is collected, or a flat monthly fee. For a small practice, percentage pricing usually fits better: the billing company is paid when you are paid, which keeps the incentive where it belongs. Flat fees are predictable but do not flex with volume.
What moves a percentage is specialty, claim volume, payer mix, and how clean the receivables are when we take them on, which is why we quote a range first and a number only after the free account review. How other companies structure their fees is covered in our guide to medical billing pricing.
50A Northwestern Drive, Salem, NH 03079
603-207-3172
(866) 906-3116
info@summitbillingsolutions.com
Mon - Fri @ 9am - 5pm
Summit Billing Solutions has been one of the best decisions for my business. They’re responsive, transparent, and make billing feel organized and manageable. They truly feel like a partner, not a vendor. Highly recommend.