


Revenue cycle management (RCM) in medical billing is the whole process a practice uses to get paid for a patient visit. It starts when the appointment is booked and ends when the last dollar from the payer and the patient is posted and reported. Medical billing is one part of that cycle: building the claim, sending it, posting the payment and working the denials. So the short answer to “medical billing vs revenue cycle management” is that billing sits inside RCM, and RCM also covers the steps before the claim exists and the analysis after it’s paid.
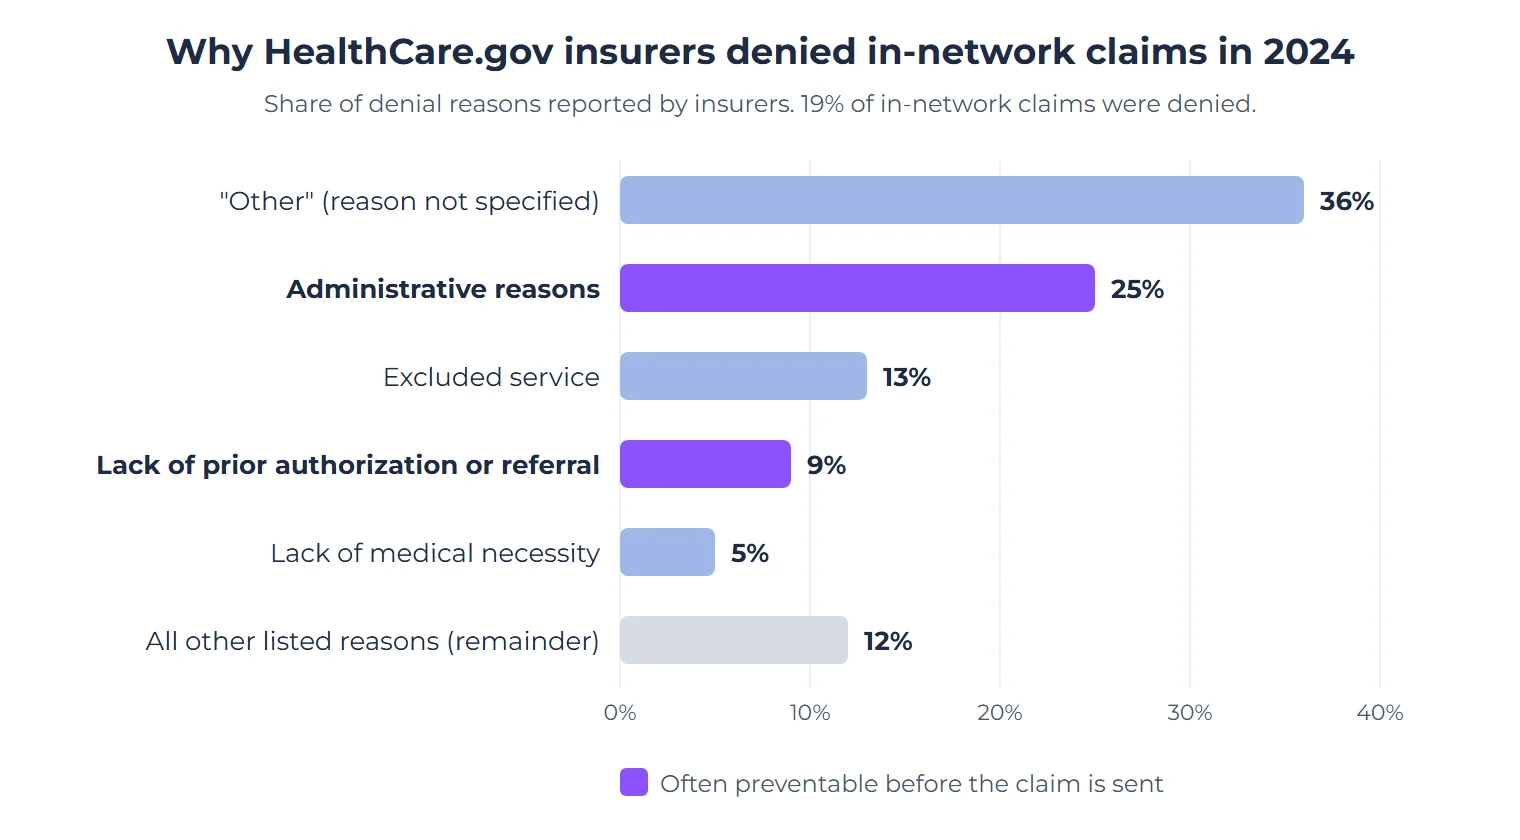
The difference matters in practice. Many claim problems start before anyone touches a claim. In KFF’s analysis of 2024 federal data, insurers on HealthCare.gov denied 19% of in-network claims, and administrative reasons such as missing information, duplicates and late filing made up 25% of the denial reasons insurers reported (KFF, March 2026). A billing team can rework those claims. A revenue cycle team also asks why they were wrong when they left the building.
This guide defines both terms, walks through the 10 steps of the revenue cycle with the rules that apply at each one, and shows which steps a billing service usually covers. It ends with the numbers that tell you whether your cycle is healthy.
Key Takeaways
- Revenue cycle management in medical billing runs from scheduling to the final patient payment. Medical billing covers the claim, payment and denial steps inside it.
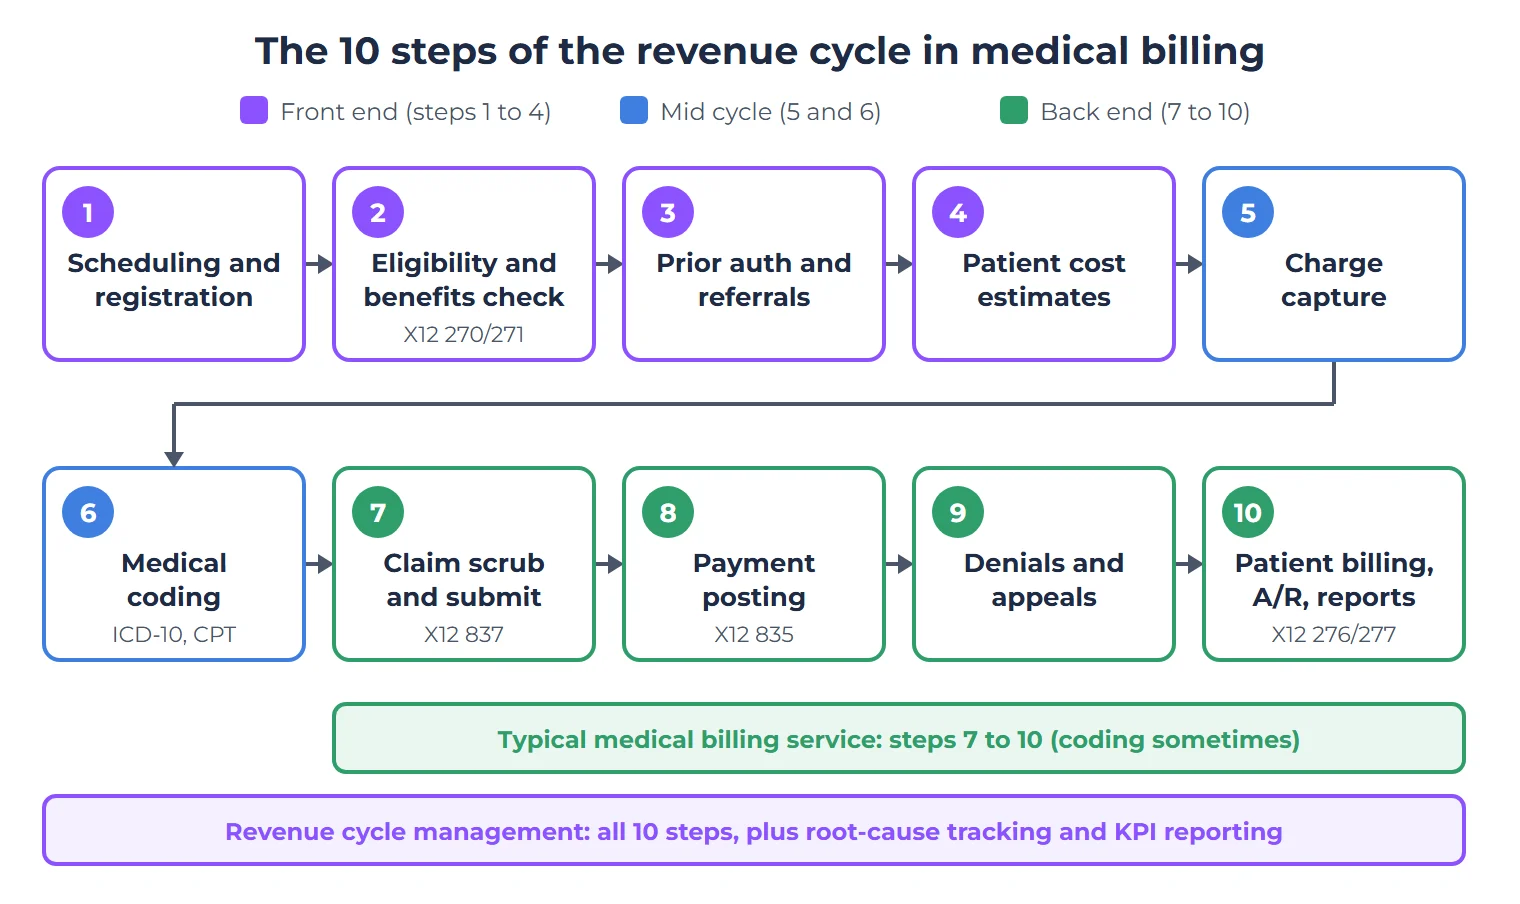
- The cycle has 10 steps: registration, eligibility, authorization, estimates, charge capture, coding, claim submission, payment posting, denials and appeals, and patient billing with A/R follow-up.
- A billing-only service usually starts at the claim. Front-end steps such as eligibility checks and prior authorization are where an RCM service adds the most.
- Medicare claims must be filed within 12 months of the date of service, and a Medicare redetermination must be requested within 120 days of the remittance advice.
- Track four numbers every month: days in A/R, net collection rate, denial rate and first-pass claim rate.
What Is Medical Billing?
Medical billing is the work of turning a documented, coded visit into a claim, getting that claim paid and collecting what the patient owes. It’s the claims and payments engine of the practice.
A medical billing team typically handles:
- Charge entry from the encounter or superbill
- Claim creation and scrubbing against payer edits
- Electronic claim submission and clearinghouse rejections
- Payment posting from the remittance advice
- Denial correction, resubmission and appeals
- Patient statements for the balance after insurance
- Follow-up on unpaid claims
On Medicare’s side, most of this travels as standard electronic transactions: the ASC X12 837 professional claim, the 835 remittance advice and the 276/277 claim status inquiry (Medicare Claims Processing Manual, chapter 24, section 10.3). Commercial payers use the same HIPAA transaction standards.
Billing is essential, because even a medically necessary service goes unpaid if the claim is late, incomplete or coded wrong. But billing starts with whatever information it is handed. If the insurance on file was inactive or the authorization was never obtained, the biller inherits the problem.
What Is Revenue Cycle Management in Medical Billing?
Revenue cycle management in medical billing is the end-to-end management of how a practice earns, bills, collects and reports revenue for each patient encounter. It begins before the visit, with registration and coverage checks, and ends after the account is paid, reconciled and measured.
RCM adds three things that billing alone does not:
- The front end. Scheduling, eligibility and benefits checks, prior authorization and patient estimates happen before a claim exists. Errors made here show up weeks later as denials.
- Ownership across departments. The front desk, the providers, the coders and the billers all touch revenue. RCM treats them as one process with one set of numbers.
- Root-cause work and reporting. A billing team fixes the denied claim. An RCM team tracks why claims are denied, by payer and reason, and changes the workflow that caused it.
That’s why RCM is sometimes described as the practice’s financial operating system, with billing as the claims engine inside it. Practices that want someone to run the whole cycle buy revenue cycle management services. Practices that only need the claims engine run buy billing.
The 10 Steps of the Revenue Cycle in Medical Billing
The revenue cycle management process in medical billing has 10 steps. Different sources group them differently, but every version covers the same ground: front end (steps 1 to 4), mid cycle (steps 5 and 6) and back end (steps 7 to 10). For how the same steps play out in one specialty, see our optometry RCM guide.
1. Scheduling and patient registration
The cycle starts when the visit is booked. The practice captures the patient’s legal name, date of birth, address, insurance card (front and back) and any referral. Every later step depends on this data, so a typo in a member ID or a missing secondary plan can sink a claim that’s coded perfectly.
2. Insurance eligibility and benefits verification
Before the visit, the practice confirms the plan is active on the date of service, the provider is in network and what the patient will owe: copay, deductible and coinsurance. Electronically, this is the X12 270/271 eligibility inquiry and response, which Medicare also supports (CMS, chapter 24). Checking again close to the visit date catches plan changes, which matter most in January after open enrollment. Our insurance eligibility verification page covers how this works day to day.
3. Prior authorization and referrals
Some services need payer approval before they’re performed. Lack of prior authorization or referral accounted for 9% of the in-network denial reasons in KFF’s 2024 data. Since January 1, 2026, CMS has required Medicare Advantage organizations, state Medicaid and CHIP programs and their managed care plans to decide standard prior authorization requests within 7 calendar days and expedited requests within 72 hours. Those payers must also offer a prior authorization API starting January 1, 2027 (CMS-0057-F fact sheet). Faster decisions only help if the request is filed and tracked, which is the job of prior authorization in the cycle.
4. Patient cost estimates and financial policy
Patients who aren’t using insurance are entitled to a good faith estimate. CMS says that when care is scheduled 3 to 9 business days ahead, the estimate is due within 1 business day, and when it’s scheduled 10 or more business days ahead, within 3 business days (CMS good faith estimate guide). For insured patients, this step is about collecting copays and known balances at check-in and explaining the practice’s payment policy before the bill arrives.
5. Charge capture and documentation
Every service performed has to appear in the medical record and on the encounter. Missed charges are the quietest leak in a revenue cycle: nothing is denied, because nothing was billed. Reconciling scheduled visits and procedures against posted charges each day closes that gap.
6. Medical coding
Coders translate the documentation into ICD-10-CM diagnosis codes, CPT and HCPCS procedure codes and any modifiers. Code sets change on a schedule. The FY2027 ICD-10-CM update took effect on October 1, 2026, with 190 new codes and 30 deletions (CMS FY2027 code descriptions), and a diagnosis that no longer supports the procedure can come back as a CO-11 denial. Coding accuracy is checked before the claim is built, which is the role of medical coding in RCM.
7. Claim creation, scrubbing and submission
The claim is built (an 837P electronically, or a CMS-1500 on paper), checked against payer edits and sent through a clearinghouse. Rejections at this stage are not denials yet; they’re claims the payer never accepted, and they need fixing within days. Deadlines apply: Medicare claims must be filed no later than 12 months, or 1 calendar year, after the date of service under 42 CFR 424.44 (Medicare Claims Processing Manual, chapter 1, section 70). Commercial payer limits are set in each contract and are often shorter.
8. Payment posting and reconciliation
When the payer adjudicates the claim, it sends an 835 remittance advice and, usually, an electronic funds transfer. Posting applies each payment, contractual adjustment and patient responsibility amount to the right line. Good posting also compares the allowed amount with the contracted rate, because an underpayment that isn’t caught here is rarely caught later. See how payment posting fits the cycle.
9. Denial management and appeals
Denied lines are sorted by reason code, corrected and resubmitted, or appealed. KFF found that consumers appealed fewer than 1% of denied in-network claims in 2024, which shows how much denied money is simply left with payers when nobody works it. For Medicare, a redetermination must be filed within 120 days of receiving the remittance advice, and the MAC generally decides within 60 days (CMS MLN006562, Medicare Parts A and B Appeals Process). The RCM part of this step is the follow-through: tracking denials by payer and reason so the same mistake stops recurring. That’s the focus of denial management.
10. Patient billing, A/R follow-up and reporting
Whatever the patient owes after insurance is billed on clear statements with payment options. Unpaid insurance claims are followed up by age, using claim status checks (276/277) and payer calls, before they pass timely filing or appeal limits. A/R recovery is the cleanup when that follow-up has fallen behind. Finally, the month’s results are reported so the practice can see where money is slowing down.
Medical Billing vs Revenue Cycle Management: Key Differences
The clearest way to compare medical billing vs revenue cycle management is to ask who owns each of the 10 steps. This is the typical split. Individual vendors draw the line in different places, so ask any partner which steps they take on.
| Step | Medical billing service | Revenue cycle management |
|---|---|---|
| 1. Scheduling and registration | Practice | Reviewed or managed |
| 2. Eligibility and benefits | Sometimes | Included |
| 3. Prior authorization | Rarely | Included or tracked |
| 4. Patient estimates | Practice | Included or supported |
| 5. Charge capture | Charge entry only | Reconciled against the schedule |
| 6. Medical coding | Sometimes, as review | Included or audited |
| 7. Claim scrubbing and submission | Included | Included |
| 8. Payment posting | Included | Included, with underpayment checks |
| 9. Denials and appeals | Claim-level fixes | Fixes plus root-cause tracking |
| 10. Patient billing, A/R and reporting | Statements and basic A/R | Full A/R, KPIs and payer trends |
In short, billing starts when a claim is ready to build. Revenue cycle management starts when the patient calls for an appointment.
Is Revenue Cycle Management the Same as Billing?
No. Billing is part of revenue cycle management, but RCM also includes the steps before a claim exists and the analysis after it’s paid.
A medical biller asks, “Was this claim submitted correctly, and did we get paid?” A revenue cycle team asks, “What happened between scheduling and final payment, and what should change so the next 100 claims are paid faster?”
Take a practice with rising denials. A billing team corrects and resubmits each one. An RCM team also looks at the pattern. Are eligibility checks being skipped on walk-ins? Is one payer denying a service the practice performs every day? Are authorizations expiring before the procedure date? The answers usually point to the front desk or a template, not to the biller.
Medical Billing vs Coding vs Revenue Cycle Management
These three are often lumped together, but they’re different jobs:
- Medical coding translates clinical documentation into standard diagnosis and procedure codes (step 6).
- Medical billing uses those codes to create claims, post payments, work denials and bill patients (steps 7 to 10).
- Revenue cycle management oversees the full process, including the front-end steps before coding and the reporting after billing (steps 1 to 10).
When these roles aren’t clearly defined, problems bounce between them. Coders get blamed for payer issues, billers for documentation gaps and the front desk for eligibility misses. A clear revenue cycle structure gives each step an owner. If you’re new to the coding side, start with our explainer on what medical coding is.
How to Measure Your Revenue Cycle
You can’t manage a revenue cycle you don’t measure. These four numbers, pulled monthly from your practice management system, show where it stands. The formulas are standard; the example figures are for illustration only.
| Metric | Formula | Illustrative example |
|---|---|---|
| Days in A/R | Total A/R ÷ average daily charges (charges for the last 90 days ÷ 90) | $180,000 ÷ ($540,000 ÷ 90) = 30 days |
| Net collection rate | Payments ÷ (charges − contractual adjustments) | $380,000 ÷ ($600,000 − $200,000) = 95% |
| Denial rate | Claims denied ÷ claims adjudicated | 90 ÷ 1,000 = 9% |
| First-pass claim rate | Claims paid on first submission ÷ claims submitted | 960 ÷ 1,000 = 96% |
Watch the trend more than any single month. A rising share of A/R older than 90 days, or a denial rate that keeps climbing for one payer, tells you which step in the cycle to look at. For reference, Summit’s own first-pass claim rate is 95% to 98%.
Which One Does Your Practice Need?
Neither service is better in the abstract. The right choice depends on where your revenue is getting stuck.
Medical billing may be enough if:
- Your front desk already verifies coverage accurately and tracks authorizations.
- Your providers document clearly and your coding is stable.
- Your denial rate is low and your A/R isn’t aging.
- You mainly need claims submitted, payments posted and unpaid claims followed up. That’s what outsourced medical billing covers.
Revenue cycle management is the better fit if:
- You don’t know where revenue is being lost.
- The same denial reasons keep coming back.
- A/R over 90 days is growing month after month.
- Eligibility or authorization errors are common.
- Your reports don’t show denials by payer and reason.
- You suspect underpayments against your contracted rates.
Many independent practices land in between. They don’t need a large RCM program, but they need more than claim submission: denial tracking, A/R follow-up and a monthly report that explains the numbers. A billing partner that also owns eligibility and denials, and reports on the whole cycle, covers that middle ground. If you need every step handled, compare what full RCM support includes. Whichever you choose, ask which of the 10 steps the partner will own, who owns the rest, and what you’ll see in the monthly report.
How Summit Approaches the Revenue Cycle
Summit Billing Solutions works inside the practice management system you already use, in any specialty, and every client signs a business associate agreement. Our RCM service runs the cycle from eligibility checks to the monthly report, and the work starts with an account analysis of your own claims, so the decision between billing support and full RCM is based on your data rather than a sales pitch.
Want to see which steps of your revenue cycle are costing you the most?
Request a free revenue cycle assessment. We’ll review your recent claims, denials and A/R by payer and show you where revenue is slowing down before you commit to anything.
Frequently Asked Questions About Revenue Cycle Management in Medical Billing
1. What is revenue cycle management in medical billing?
Revenue cycle management in medical billing is the full process a practice uses to get paid for patient care, from scheduling and eligibility checks before the visit to coding, claim submission, payment posting, denial management and patient collections afterward. Medical billing is the claims and payments part of that cycle.
2. Is revenue cycle management the same as medical billing?
No. Medical billing is one part of revenue cycle management. Billing focuses on creating and submitting claims, posting payments and working denials. RCM also covers the front-end steps before the claim, such as eligibility verification and prior authorization, and the reporting and root-cause work after payment.
3. What are the steps of the revenue cycle in medical billing?
The 10 steps are scheduling and registration, eligibility and benefits verification, prior authorization and referrals, patient cost estimates, charge capture, medical coding, claim creation and submission, payment posting, denial management and appeals, and patient billing with A/R follow-up and reporting.
4. What is the main difference between medical billing and RCM?
Scope. Medical billing usually starts when a claim is ready to be built and ends when it is paid. Revenue cycle management starts when the appointment is scheduled and ends when the account is paid, reconciled and reported, and it includes fixing the causes of denials, not just the denied claims.
5. Which KPIs show how well a revenue cycle is working?
Four core metrics are days in A/R, net collection rate, denial rate and first-pass claim rate. Track them monthly and by payer. A growing share of A/R older than 90 days or a rising denial rate for one payer points to the step in the cycle that needs attention.