


Credentialing is not the same as enrollment, and the difference matters for the calendar. Credentialing is the plan deciding whether a provider may join its network. Enrollment is the paperwork that makes a credentialed provider payable: Medicare’s PECOS application, the plan’s provider record, electronic claims, remittance and payment setup, and the revalidation cycle after that. CMS runs Medicare enrollment through PECOS, its online enrollment system. Summit Billing Solutions does both, and describes the enrollment side on its own page, payer enrollment, because they are different work with different deadlines.
What credentialing decides is money. A provider who sees patients before the plan’s effective date is out of network for those visits, whatever the practice intended, and most plans will not pay those claims at in-network rates or at all. That is why the work starts the day a provider signs, not the day they start, and why every application is tracked to a date rather than to a submission. Our guide to credentialing in medical billing for small practices covers the background.
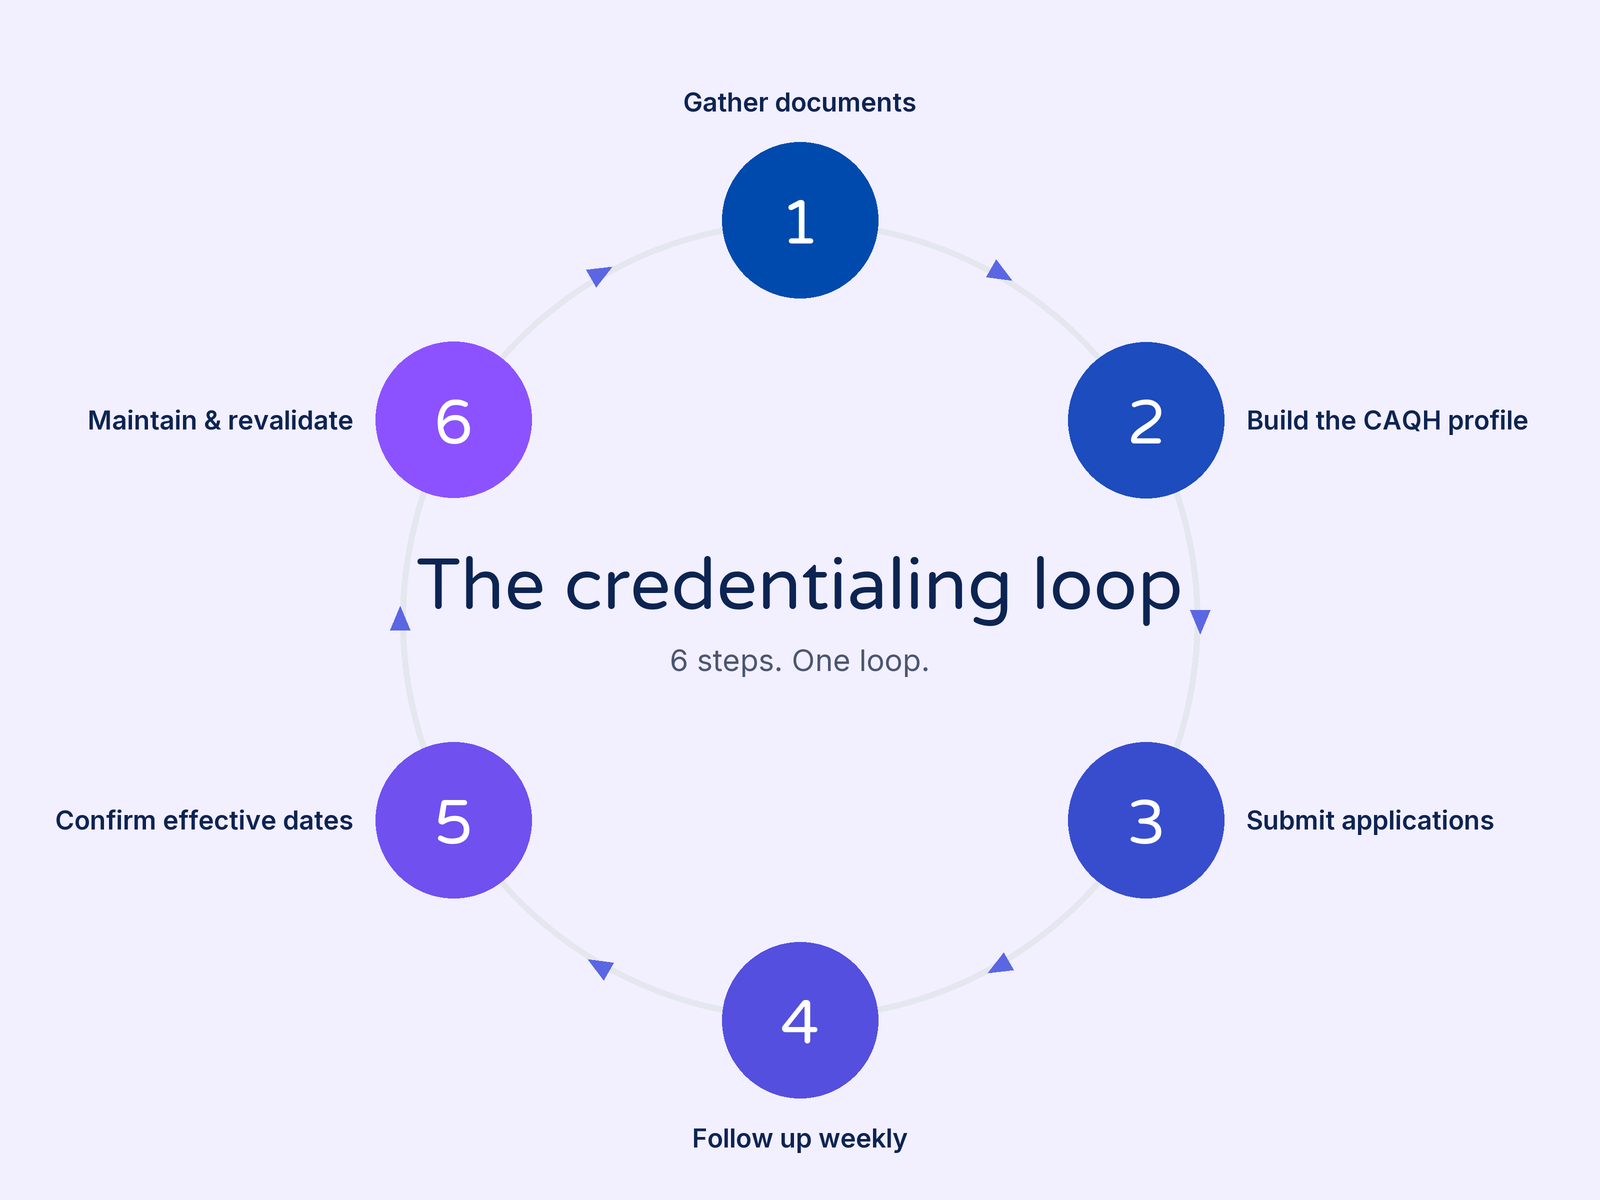
| Number | Step | What happens | Where it stalls, and what we do | Related service |
|---|---|---|---|---|
| 1 | Gather the documents | State licence, DEA registration, board certification, diplomas, malpractice certificate and claims history, work history without gaps, NPI, and the practice's tax and location details. | One missing document holds every application. We send the provider one checklist, collect everything once, store it securely, and flag expiry dates before they become a problem. | Free account review |
| 2 | Build the CAQH profile | Most commercial plans pull the provider's data from the CAQH provider data portal instead of asking for it again. The profile is created or updated, documents uploaded, and the plans authorised to read it. | A profile with an unanswered question or an expired attestation is invisible to the plan, and nobody tells the practice. We complete it fully and keep it attested on the portal's schedule. | CAQH maintenance |
| 3 | Submit the applications | Each plan gets its own application, on its own form or portal, with the documents and the CAQH authorisation it asks for. Medicare and Medicaid go through their enrollment systems. | Applications sent without a confirmation number are the ones that vanish. We record the submission date, the reference and the contact for every plan, and we submit them in the order the practice needs them. | Payer enrollment |
| 4 | Verification and committee review | The plan verifies each credential at its source, checks sanctions and malpractice databases, and puts the file to a credentialing committee that meets on its own calendar. | Requests for one more document sit in an inbox for a month. We call every open application weekly, answer requests the same day, and escalate when a plan's own stated timeline passes. | Weekly follow-up |
| 5 | Contract and effective date | The plan issues a participation agreement or adds the provider to an existing group contract, and states the effective date from which in-network claims will pay. | The letter names an effective date later than the provider's first patient, and those visits are out of network. We confirm the date in writing, load it into the billing system, and tell scheduling before the first appointment. | Medical billing |
| 6 | Re-credentialing and revalidation | Plans re-credential on a fixed cycle and Medicare requires revalidation; CMS states that providers and suppliers revalidate every five years, DMEPOS suppliers every three. | A missed revalidation deactivates billing privileges, and the claims stop paying until it is fixed. We keep a calendar of every plan's cycle and start the renewal before the plan's notice arrives. | Revalidation |
| Compare | Office manager, part-time | Summit Billing Solutions |
|---|---|---|
| Documents | Collected plan by plan, with the same certificate requested three times. | Collected once from a single checklist, stored securely, with expiry dates tracked. |
| Applications | Submitted when time allows, sometimes without a reference number. | Submitted in the order the practice needs, each with its date, reference and contact recorded. |
| Follow-up | When the provider asks why claims are denying. | Every open application called weekly; the plan's requests answered the same day. |
| Effective dates | Discovered from the first denial. | Confirmed in writing, loaded into billing, and sent to scheduling before the first visit. |
| CAQH and revalidation | Attested when a plan complains. | Attested on schedule, documents renewed before expiry, revalidation started before the notice. |
| Visibility | Whatever is in the manager's inbox. | A status for every provider and every plan, reviewed on the weekly call. |
We list every provider and every plan you bill, show which combinations are credentialed, pending or missing, and pull the revalidation and attestation dates coming up, whether or not you go further with us.
Each provider gets one checklist. We collect the licences, certificates, history and identifiers once, build or update the CAQH profile, and confirm the practice's tax and location details match across every application.
Applications go to each plan in the order you need them, with the date and reference logged. Every open application is called weekly, requests are answered the same day, and effective dates are confirmed in writing and loaded into your billing system.
After approval the work continues: CAQH attestations on schedule, documents renewed before expiry, revalidations started early, and a status for every provider and plan on your weekly call.


Your claims are worked by a team in the United States, not routed offshore.
You know who is working your account, and you hear from them every week. A familiar face, not a ticket queue.
If we are not earning the relationship, you can leave. That keeps us honest.
We are in Salem, NH, and we bill for practices nationwide, with the state-by-state payer knowledge that takes.
2%
Average claim rejection rate
24 hrs
Claims submitted within
28
Average days in A/R

I’ve been in billing for 30+ years and Summit is the best I’ve worked with. They’re knowledgeable, detailed, and persistent to get claims paid instead of writing them off. They take the burden off providers so we can focus on patients.

We billed in-house for decades, but it was time for a change. I couldn’t be happier with Summit. The transition was seamless thanks to their strong systems and clear communication. If you’re considering a switch, talk to Summit.


When Summit Billing Solutions handles your billing, credentialing a provider who joins the practice is part of the service, inside the fee of 3% to 9% of monthly collections, because an uncredentialed provider produces claims that cannot pay.
A practice that keeps its billing in house can have credentialing alone. That is quoted per provider and per plan after the free account review, once we know how many providers, how many plans, and how many of those are new applications rather than maintenance. We do not promise a turnaround, because the plan sets it; we promise that every application is followed weekly until it has a date. How billing companies structure their fees more generally is covered in our guide to medical billing pricing.
50A Northwestern Drive, Salem, NH 03079
603-207-3172
(866) 906-3116
info@summitbillingsolutions.com
Mon - Fri @ 9am - 5pm
Summit Billing Solutions has been one of the best decisions for my business. They’re responsive, transparent, and make billing feel organized and manageable. They truly feel like a partner, not a vendor. Highly recommend.