

Pulmonology billing services for office visits, lung testing and bronchoscopy

Pulmonology billing for practices and groups: office visits, pulmonary function testing, bronchoscopy and EBUS, sleep studies, biologics for severe asthma, and hospital and critical care, worked inside the software you already use by a US-based team.

Physician talking with a patient in a clinic exam room
Google logo
Rated 4.9 on Google★★★★★

What pulmonology billing services include

Pulmonology billing services turn every visit, test and procedure into a paid claim. Each pulmonary function test is coded to what was performed, procedures are coded by technique and site, hospital work is billed by the rules for each setting, and every payment, denial and patient balance is followed until it is resolved.

$179M

in improper Medicare payments to pulmonary disease in CMS’s 2025 review, a 14.4% improper payment rate

47.3%

of those pulmonary errors were incorrect coding, and another 36.6% were missing or insufficient documentation

Pulmonology bills tests that nest inside each other. Spirometry is part of the before-and-after bronchodilator study, diffusion capacity is an add-on to the test it was done with, and pulse oximetry is usually not paid on its own. Add bronchoscopies coded by each technique and site, sleep studies split between the lab and the reader, and critical care billed by the minute in the hospital, and the same patient can generate claims in three settings in one week.

What was performed, and where, decides the claim. That is why we check every test against what it includes and every procedure against the report before the claim goes out, not after it is bundled or denied.

Three kinds of pulmonology claims, three sets of rules

Most pulmonology practices bill lung testing, procedures and hospital care in the same week, often for the same patient. Each one pays differently and fails in its own way. Here is where each breaks, and what we do about it.

Pulmonary function testing

Pays forSpirometry, bronchodilator studies, lung volumes, diffusion capacity and walk tests, done in your office or read for a hospital lab.

Where it breaks

What we do

Bronchoscopy and procedures

Pays forDiagnostic and therapeutic bronchoscopy, EBUS-guided sampling, navigation, and the moderate sedation that supports them.

Where it breaks

What we do

Sleep, hospital and critical care

Pays forHome and lab sleep studies, hospital visits, and critical care time in the ICU.

Where it breaks

What we do

Pulmonary function tests: billing what each test includes

Pulmonary function tests are coded by the most complete study done, and many of them include smaller ones. Spirometry before and after a bronchodilator (94060) includes simple spirometry (94010), so the two are not billed together. Lung volumes are measured by plethysmography (94726) or by gas dilution (94727), and diffusion capacity (94729) is an add-on billed with the spirometry or lung volume test it was done with. The bronchodilator drug can be billed on its own line, but the treatment given during the test is part of it.

Medicare pays pulse oximetry (94760 and 94761) only when no other service is billed for the patient that day, so it should not be expected as a separate payment with a visit or a full test panel. When the test is run on hospital equipment, the practice bills only the interpretation, with modifier 26.

What we do: before a PFT claim goes out, we compare the codes with the tests in the report, remove the ones a larger test includes, add the diffusion and drug lines that apply, and check who owns the equipment. If anything does not match, we fix it the same day.

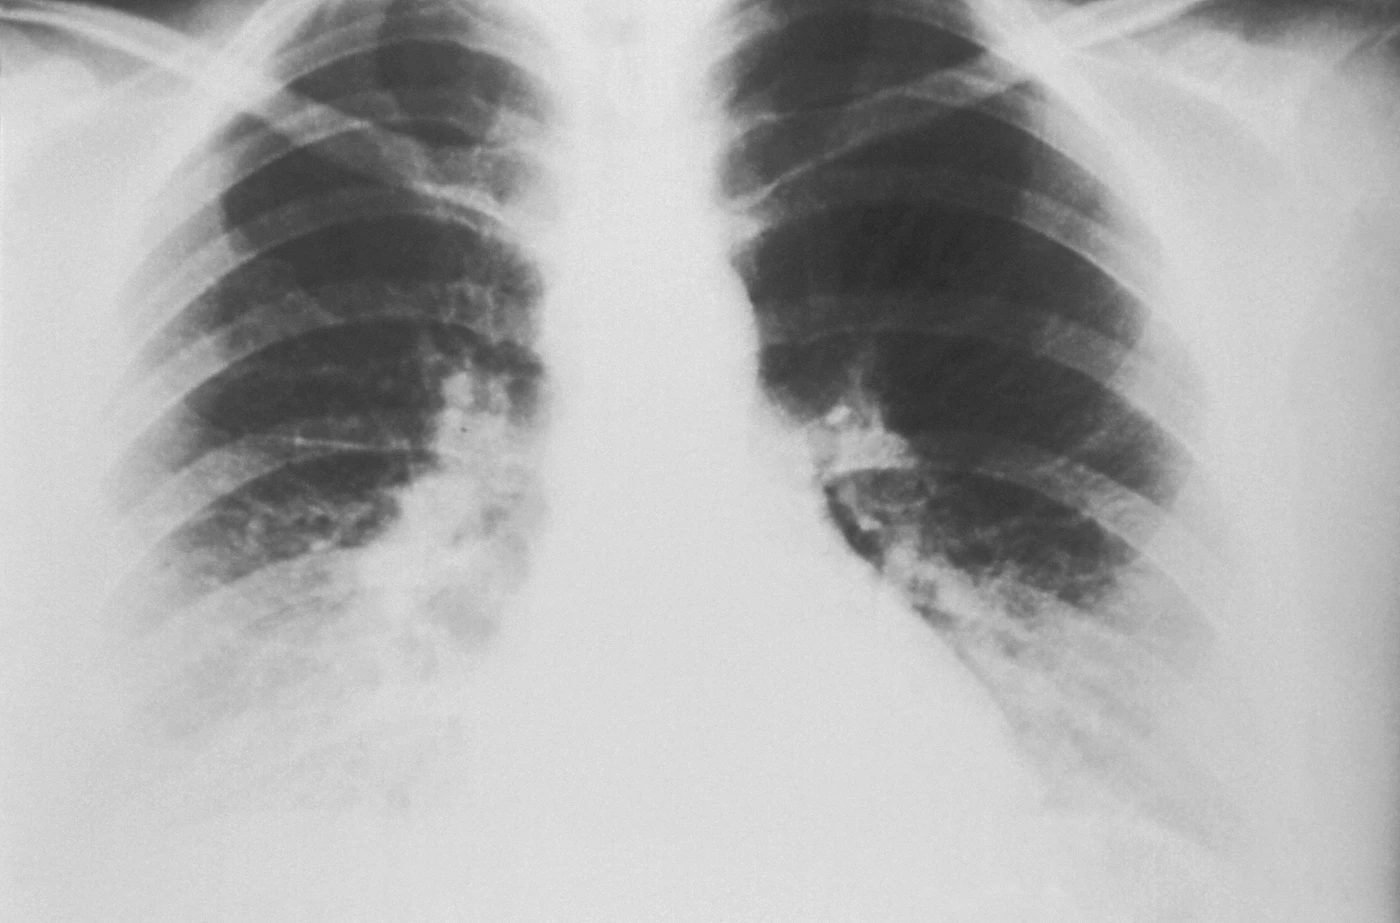
Chest X-ray showing both lungs
Pulmonary function test billing checklist

Before you bill

  1. Tests: each study performed: spirometry, bronchodilator response, lung volumes, diffusion, walk test
  2. Method: plethysmography or gas dilution for lung volumes
  3. Drug: the bronchodilator and dose given during the test
  4. Setting: your equipment, or a hospital lab where you only interpret

What goes on the claim

  1. Spirometry: 94010, or 94060 when a bronchodilator was given, never both
  2. Volumes and diffusion: 94726 or 94727, with 94729 as the add-on for diffusion
  3. Oximetry: 94760 or 94761 only when it is the only service that day for Medicare
  4. Reading only: modifier 26 for studies on hospital equipment
Sources: Medicare NCCI Policy Manual, chapter XI (medicine); Medicare Physician Fee Schedule status indicators; CMS, 2025 Medicare Fee-for-Service Supplemental Improper Payment Data.

The pulmonology codes and modifiers we bill every day

These are the codes behind most pulmonology claims, and what payers look for on each one. Commercial plans add their own authorization and bundling rules, and we check each one.

Pulmonology codes and what payers look for
CodeWhat it coversWhat payers look for
99202 to 99215Office visits (E/M)The level matches the decision making or time documented; modifier 25 with a same-day procedure only when the visit is separate.
9401094060Spirometry, and spirometry before and after a bronchodilator94060 includes 94010; the bronchodilator drug billed on its own line.
947269472794729Lung volumes and diffusion capacity94729 is an add-on to the spirometry or lung volume test done with it.
94618Six-minute walk testIncludes the oximetry done during the walk.
31622316243162531628Bronchoscopy: diagnostic, lavage, bronchial biopsy and transbronchial lung biopsyEach technique coded when performed; 31628 for one lobe and 31632 for each additional lobe.
316523165331654EBUS-guided sampling31652 for one or two lymph node stations, 31653 for three or more, 31654 for radial EBUS of a peripheral lesion.
9581095811Sleep studies in a lab, without and with CPAP titrationSplit into 26 and TC when the lab and the reading are billed by different providers.
95806G0399Home sleep apnea testsThe code that matches the device used; many plans require a home test before a lab study.
9929199292Critical careFrom documented time of 30 minutes or more, excluding time on separately billed procedures.
J2357J2182J0517Biologics for severe asthma given in the officeAuthorization, units from the dose given, and JZ or JW on single-dose vials.

Modifiers that decide the claim

26

Professional part

The reading of a PFT or sleep study done on hospital or another provider's equipment.

TC

Technical part

The equipment and staff portion, when another physician reads the study.

25

Separate visit

An office visit that is significant and separate from a same-day procedure or test. Modifier 25 explained

59 / XS

Separate site

Procedures not normally billed together, done at separate sites. Our modifier 59 guide

JZ

No drug discarded

Required by Medicare on single-dose drugs when the whole dose was given.

JW

Drug discarded

The unused part of a single-dose vial, billed on its own line.

Sources: Medicare NCCI Policy Manual, chapter V (respiratory system) and chapter XI (medicine); Medicare Claims Processing Manual, chapter 12 (physician services, including critical care); CMS JW and JZ Modifier FAQs. CPT is a registered trademark of the American Medical Association; the descriptions above are summaries. Reviewed October 2026.

Who pulmonology billing services are for

It is not for every practice. If you are a hospital-employed group whose billing the hospital handles, you do not need us. And if your in-house team keeps denials low and receivables current, keep them, and consider a periodic billing audit instead.

How we take over your billing

  1. Free account review

    We look at your clean-claim rate, your denials by payer and reason, PFT bundling, bronchoscopy coding, sleep study components, hospital charges, and your aging receivables, and tell you what we find, whether or not you go further with us.

  2. Onboarding

    We get access to your practice management system and clearinghouse, load each payer's authorization and bundling rules and your fee schedules, list open authorizations and hospital rounding schedules, and agree how escalations work. Most practices are live within one to two weeks.

  3. Daily billing

    Visits, tests and procedures are coded and claims submitted within 24 hours. Rejections are corrected the same day, remittances posted as they arrive, test bundling, components and hospital charges checked, and denials worked to their cause, all inside your system.

  4. Monthly reporting

    A report you can read in ten minutes: what was billed and collected by payer, site and service line, what was denied and why, authorizations pending, and what is aging.

We work with your software

You do not change systems to work with Summit Billing Solutions. We work in the practice management and EHR systems below, and through the clearinghouse you already use. If your EHR is not shown, ask; the list grows as we onboard practices.

athenahealth EHR and revenue cycle management software logo
eClinicalWorks EHR software logo
NextGen Healthcare EHR software logo
Allscripts EHR software logo
HealthFusion MediTouch EHR software logo
CureMD EHR and practice management software logo
AdvancedMD practice management and medical billing software logo
Tebra practice management and medical billing software logo
Availity clearinghouse logo
Office Ally clearinghouse and practice management software logo

Why pulmonology practices choose Summit Billing Solutions

Pulmonology rules, applied daily

Your claims are worked by billers who handle PFT bundling, bronchoscopy and EBUS coding, sleep study components and critical care time every day, not once a quarter.

A named contact and a weekly call

You know who is working your account, and you hear from them every week. A familiar face, not a ticket queue.

Month to month, no long-term lock-in

If we are not earning the relationship, you can leave. That keeps us honest.

A US-based team, serving all 50 states

Your claims are worked in the United States, with the state-by-state payer and Medicaid knowledge that takes.

Results and reviews

2%

Average claim rejection rate

24 hrs

Claims submitted within

28

Average days in A/R

Billing can easily become stressful and overwhelming, but with their team, the entire process feels organized, manageable, and under control.

Matthew Hersey
Matthew Hersey

Not only have they helped us streamline our operations, but their expertise has also maximized our revenue cycle, allowing us to focus more on patient care. The level of communication is outstanding; we always feel informed and supported.

Khadijah Cisse
Khadijah Cisse

Their organization and communication skills are impressive, allowing for effective and efficient collaboration.

Alan Almanzar
Alan Almanzar

Google logo
Rated 4.9 out of 5
Rated 4.9 by our clients on Google

How pulmonology billing pricing works

Most billing companies charge a percentage of what they collect; some charge a flat monthly fee or a per-claim rate. For a pulmonology practice, a percentage usually fits best: the company is paid when you are paid, so the incentive sits where it belongs.

Summit Billing Solutions charges between 3% and 9% of monthly collections. What moves the number for a pulmonology practice is the mix of office, procedure and hospital work, how many tests you run and read, authorization volume, and how clean the receivables are when we take them on, which is why we quote your exact rate after the free account review, not before.

3% to 9%

of monthly collections

Questions pulmonology practices ask before switching

Most billing companies charge a percentage of collections, and a few charge a flat monthly or per-claim fee. Summit Billing Solutions charges between 3% and 9% of monthly collections. For a pulmonology practice, the rate depends on the mix of office, procedure and hospital work, how many tests you run and read, authorization volume and the state of your receivables, and we quote your exact rate after the free account review.

Find out what your pulmonology billing is actually costing you

A free account review looks at your clean-claim rate, your denials by payer and reason, PFT and procedure coding, sleep studies and hospital charges, and your aging receivables, and tells you what we would change. No cost, no obligation, and no pressure to continue. What the review covers, step by step, is on the free account review page.

50A Northwestern Drive, Salem, NH 03079

603-207-3172

(866) 906-3116

info@summitbillingsolutions.com

Mon - Fri @ 9am - 5pm
