

Pain management billing for practices and groups: epidural, facet and sacroiliac joint injections, radiofrequency ablation and stimulator trials, office visits and urine drug testing, worked inside the software you already use by a US-based team.


Pain management billing services turn every visit, injection and procedure into a paid claim. Each injection is coded to the level, side and guidance documented, coverage rules for diagnostic and therapeutic sessions are checked before the procedure, and every payment, denial and patient balance is followed until it is resolved.
72%
of sampled sacroiliac joint injection sessions that Medicare paid did not meet its requirements, in an OIG audit published in August 2026
$15.2M
in estimated improper Medicare payments for those injections in one year, with 46,711 sessions billed as therapeutic that should have been diagnostic
Pain management is paid on rules about the patient’s response. Medicare contractors cover spinal injections only for documented indications, under image guidance, within limits on how many sessions a patient can have in a rolling 12 months, and a therapeutic injection usually depends on how much relief a diagnostic one gave. Add radiofrequency ablation and stimulator trials that need authorization, bilateral and multilevel coding, and drug testing with its own frequency rules, and the documentation decides most claims before the code does.
The pain scores and session counts decide the claim. That is why we check the indication, the imaging, the relief documented and the patient’s session history on every injection claim before it goes out, not after it is denied or recouped.
Most pain practices bill spinal injections, ablations and office visits with drug testing in the same week, often for the same patient. Each one pays differently and fails in its own way. Here is where each breaks, and what we do about it.
Pays forEpidural steroid injections, facet joint injections and nerve blocks, and sacroiliac joint injections, under fluoroscopy or CT guidance.
Where it breaks
What we do
Pays forRadiofrequency ablation of the facet joint nerves, and spinal cord stimulator trials and implants, usually after prior authorization.
Where it breaks
What we do
Pays forOffice visits for medication management, trigger point injections, and urine drug testing for patients on controlled medications.
Where it breaks
What we do
Five of the seven Medicare contractors have coverage rules for sacroiliac joint injections, and they follow the same pattern. A diagnostic injection comes first, to show the joint is the source of the pain. A therapeutic injection is covered only after a diagnostic one gave at least 75% relief, and a repeat therapeutic injection only when the last one gave at least 50% relief or better function for at least three months. Coverage is limited to two diagnostic and four therapeutic sessions in a rolling 12 months.
Each session has to be done under CT or fluoroscopy with contrast, unless a contrast allergy is documented, and the note has to record the pain level at the start and the end. Diagnostic injections are billed with modifier KX on each line. In its 2026 audit, the OIG found that a quarter of the sampled sessions were billed as therapeutic when they were diagnostic.
What we do: before an injection is scheduled, we check the patient’s diagnostic and therapeutic sessions in the past 12 months and the relief documented. Before the claim goes out, we confirm the imaging, the pain scores and modifier KX on diagnostic lines, and fix anything missing the same day.
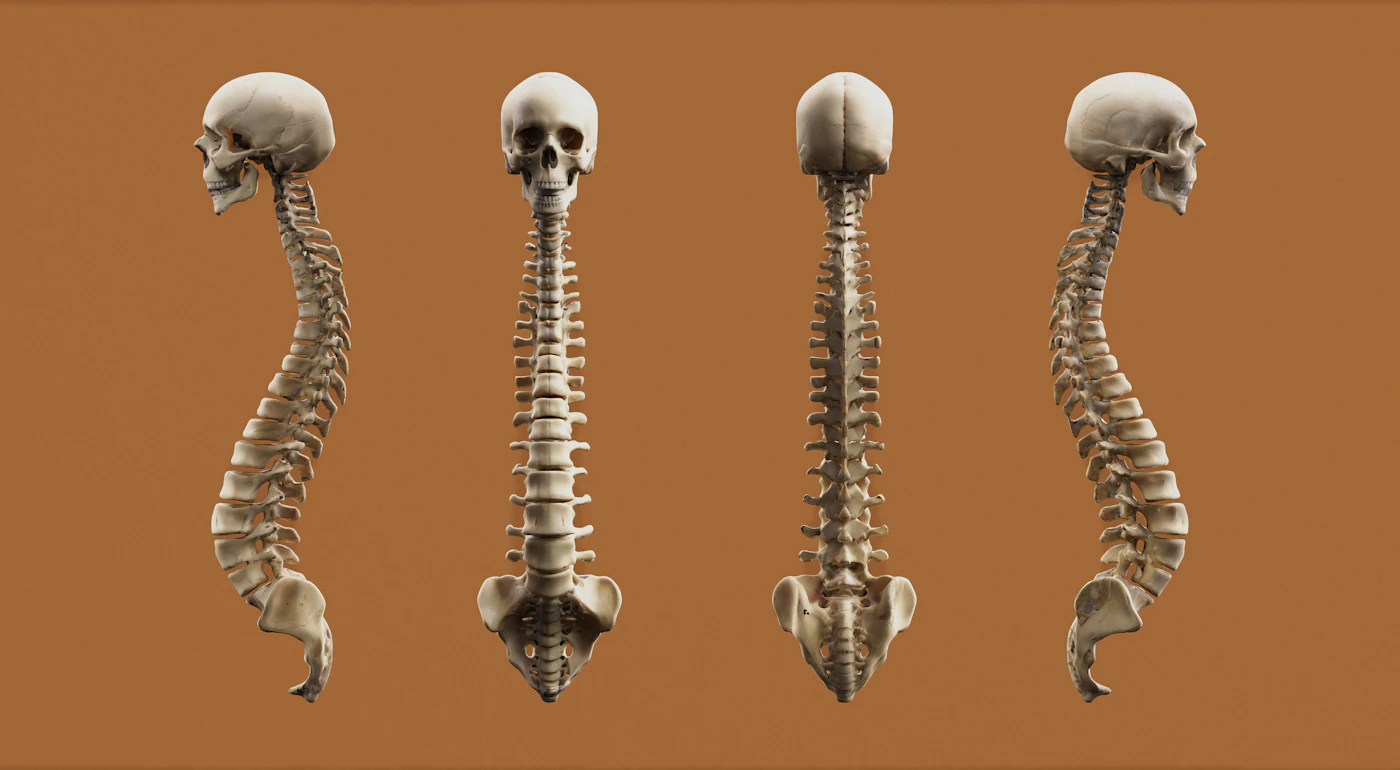
These are the codes behind most pain management claims, and what payers look for on each one. Commercial plans add their own authorization and bundling rules, and we check each one.
| Code | What it covers | What payers look for |
|---|---|---|
| 99202 to 99215 | Office visits (E/M) | The level matches the decision making or time documented; modifier 25 with a same-day procedure only when the visit is separate. |
| 6232162323 | Interlaminar epidural injections with imaging, cervical or thoracic and lumbar or sacral | Imaging included; the level, approach and drug documented; session limits by spinal region. |
| 64479 to 64484 | Transforaminal epidural injections | Billed for the first level with add-on codes for each additional level, imaging included; 50 when bilateral. |
| 64490 to 64495 | Facet joint injections and medial branch blocks | Billed by level and side with imaging included, and the diagnostic or therapeutic purpose documented. |
| 64633 to 64636 | Radiofrequency ablation of facet joint nerves | By joint level, after diagnostic blocks; authorization from many plans and limits on repeat ablations. |
| 27096 | Sacroiliac joint injection | KX on diagnostic injections; two diagnostic and four therapeutic sessions in a rolling year under Medicare coverage rules. |
| 64451 | Injection of the nerves to the sacroiliac joint | Image guidance included; the same diagnostic and therapeutic rules as 27096. |
| 2055220553 | Trigger point injections | By number of muscles: one or two, or three or more; billed once per session. |
| 63650 | Spinal cord stimulator electrode placement, percutaneous | Usually authorized in advance, with a trial before the permanent implant. |
| 80305 to 80307 | Presumptive urine drug testing | By method; ordered for a documented clinical reason, not as a routine panel. |
| G0480 to G0483 | Definitive drug testing for Medicare | Coded by the number of drug classes tested; CPT 80320 to 80377 are not used for Medicare. |
Medicare billing articles: added to each diagnostic sacroiliac joint injection line, never to therapeutic ones.
The same injection on both sides at the same level, billed the way the payer requires.
The side treated, when only one side is injected or the payer wants each side on its own line.
An office visit that is significant and separate from a same-day injection. Modifier 25 explained
A procedure on a different spinal region or site from another procedure the same day. Our modifier 59 guide
Medicare: JZ when the whole vial of a single-dose drug was used, or a JW line for the amount discarded.
Sources: HHS OIG report OAS-25-09-021; Medicare local coverage determinations for epidural steroid injections, facet joint interventions and sacroiliac joint injections, with their billing articles; Medicare NCCI Policy Manual, chapter IV (musculoskeletal system) and chapter VIII (nervous system); CMS JW and JZ Modifier FAQs. CPT is a registered trademark of the American Medical Association; the descriptions above are summaries. Reviewed October 2026.
It is not for every practice. If you are a hospital-employed group whose billing the hospital handles, you do not need us. And if your in-house team keeps denials low and receivables current, keep them, and consider a periodic billing audit instead.
We look at your clean-claim rate, your denials by payer and reason, injection documentation and session limits, drug testing, authorizations, and your aging receivables, and tell you what we find, whether or not you go further with us.
We get access to your practice management system and clearinghouse, load each payer's authorization and bundling rules and your fee schedules, list open authorizations and each patient's recent injection sessions, and agree how escalations work. Most practices are live within one to two weeks.
Visits, injections and procedures are coded and claims submitted within 24 hours. Rejections are corrected the same day, remittances posted as they arrive, pain scores, imaging and session limits checked, and denials worked to their cause, all inside your system.
A report you can read in ten minutes: what was billed and collected by payer, site and service line, what was denied and why, authorizations pending, and what is aging.
You do not change systems to work with Summit Billing Solutions. We work in the practice management and EHR systems below, and through the clearinghouse you already use. If your EHR is not shown, ask; the list grows as we onboard practices.


Your claims are worked by billers who handle injection coverage rules, KX and bilateral coding, ablation authorizations and drug testing every day, not once a quarter.
You know who is working your account, and you hear from them every week. A familiar face, not a ticket queue.
If we are not earning the relationship, you can leave. That keeps us honest.
Your claims are worked in the United States, with the state-by-state payer and Medicaid knowledge that takes.
2%
Average claim rejection rate
24 hrs
Claims submitted within
28
Average days in A/R

Not only have they helped us streamline our operations, but their expertise has also maximized our revenue cycle, allowing us to focus more on patient care. The level of communication is outstanding; we always feel informed and supported.

Their organization and communication skills are impressive, allowing for effective and efficient collaboration.

Most billing companies charge a percentage of what they collect; some charge a flat monthly fee or a per-claim rate. For a pain management practice, a percentage usually fits best: the company is paid when you are paid, so the incentive sits where it belongs.
Summit Billing Solutions charges between 3% and 9% of monthly collections. What moves the number for a pain management practice is the mix of office, injection and surgery center work, procedure volume, authorization volume, and how clean the receivables are when we take them on, which is why we quote your exact rate after the free account review, not before.
3% to 9%
of monthly collections
We bill for more than 40 specialties, for practices in all 50 states, from Salem, New Hampshire. Each one has its own codes, modifiers and payer rules.
Chiropractic billing

Family practice billing

Pediatric billing

Urgent care billing

Ophthalmology billing

Mental health billing

Psychiatry billing

Cardiology billing

Gastroenterology billing

Urology billing

Neurology billing

Dermatology billing

Pulmonology billing

Podiatry billing

Oncology billing

Orthopedic billing

OB/GYN billing

Radiology billing

Telemedicine billing
All 40+ specialties
A free account review looks at your clean-claim rate, your denials by payer and reason, injection documentation and session limits, drug testing and authorizations, and your aging receivables, and tells you what we would change. No cost, no obligation, and no pressure to continue. What the review covers, step by step, is on the free account review page.
50A Northwestern Drive, Salem, NH 03079
603-207-3172
(866) 906-3116
info@summitbillingsolutions.com
Mon - Fri @ 9am - 5pm
Billing can easily become stressful and overwhelming, but with their team, the entire process feels organized, manageable, and under control.