


G2211 is a Medicare add-on code that pays a little extra on an office or outpatient visit, and since January 2026 on a home or residence visit, when the practitioner is the patient’s continuing focal point for care or is managing a single serious or complex condition over time. It is billed on the same claim as the visit code, CMS requires no extra documentation for it, and in 2026 it is worth about $17 a visit nationally before geographic adjustment.
Most practices that could bill it still don’t. Of the 855,265 clinicians who billed a G2211-eligible visit in 2024, only 24.0% billed G2211 at all (Ganguli et al., JAMA, February 2026). The code is also about to change. On November 4, 2026, CMS finalized replacing G2211 with modifier B1 for dates of service from January 1, 2027, with a second modifier, B2, for clinicians in a Medicare ACO (CMS fact sheet, November 4, 2026). This guide covers who can bill G2211, when it applies, what the record should show, and how the switch to B1 works. Our guide to the 2027 Medicare physician fee schedule final rule covers the rest of the rule.
Key Takeaways
- Any practitioner who can bill office or outpatient E/M codes (99202 to 99205, 99211 to 99215) or home or residence E/M codes may add G2211, regardless of specialty. The test is the ongoing relationship with the patient, not the diagnosis.
- Medicare denies G2211 on a visit billed with modifier 25, except when the same-day service is an annual wellness visit, a vaccine administration or another Part B preventive service.
- CMS requires no extra documentation for G2211, but reviewers use the assessment, plan and diagnoses to confirm the ongoing relationship.
- In 2026, G2211 is worth 0.52 RVUs, about $17.37 a visit nationally. From January 1, 2027, modifier B1 on the E/M line replaces it under the same rules, and clinicians in a Shared Savings Program or LEAD Model ACO can use modifier B2.
- CMS describes B1 as a 16% increase to the visit, but its own crosswalk file adds 16% of the work RVUs only. Confirm your contractor’s 2027 rates before you load B1.
Here for modifier B1 and B2? Jump to what changes in 2027 or straight to how much B1 will pay.
What is G2211?
G2211 is a HCPCS add-on code for “visit complexity inherent to evaluation and management” when the visit is part of an ongoing relationship: either the practitioner is the continuing focal point for all of the patient’s health care services, or the practitioner provides ongoing care for a single, serious condition or a complex condition. CMS says the code captures the complexity that comes from “the longitudinal nature of the practitioner and patient relationship” (CMS G2211 FAQs).
The complexity is not in the patient’s condition on that day. CMS’s own example is a primary care practitioner treating sinus congestion: the problem is simple, but being responsible for all of that patient’s care, and using the relationship to decide how to treat and how to explain it, makes the visit inherently more complex. In that example, the practitioner may bill G2211 (MLN Matters MM13473).
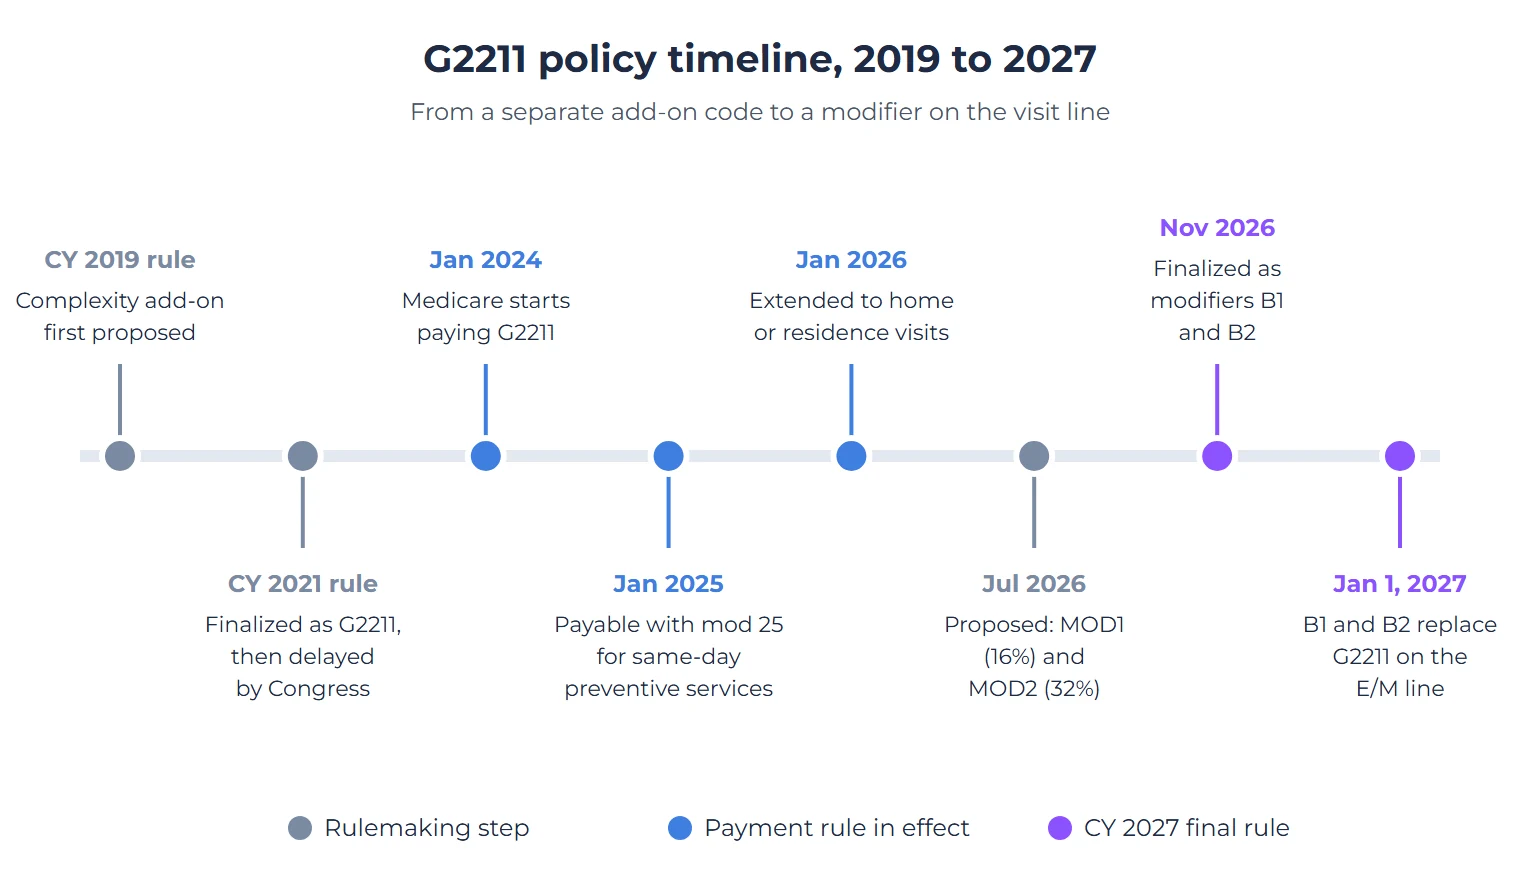
The code took years to reach a claim. CMS first proposed complexity add-ons in the CY 2019 rule cycle, finalized the code for 2021, and then Congress delayed it in the Consolidated Appropriations Act, 2021. Medicare started paying for G2211 on January 1, 2024. Three years later it becomes a modifier (CY 2027 PFS final rule).
Who can bill G2211?
Any physician or practitioner who can bill Medicare for office or outpatient E/M visits or home or residence E/M visits can report G2211, and CMS does not limit it by specialty (CMS G2211 FAQs). That includes nurse practitioners and physician assistants billing under their own NPI, and specialists who manage a condition over time.
The base code decides whether G2211 is even possible. The same base codes carry over to modifier B1 in 2027:
| Setting | Base codes | Can G2211 be added? |
|---|---|---|
| Office or outpatient visit | 99202 to 99205, 99211 to 99215 | Yes, at any level, since 2024 |
| Home or residence visit | 99341, 99342, 99344, 99345, 99347 to 99350 | Yes, since January 1, 2026 |
| Hospital inpatient, emergency department, nursing facility | Other E/M families | No |
| FQHC or RHC | Encounter-based payment | No separate payment; it is bundled into the encounter rate |
A few situations come up often in practices:
- Another clinician in your group sees the patient. If the patient has an ongoing relationship with a care team in the practice, and the other requirements are met, the covering colleague may be able to report G2211 (CMS G2211 FAQs, Q3).
- Teaching settings. G2211 can be billed for visits billed under the primary care exception (modifier GE) when its criteria are met.
- Care management in the same month. G2211 can be billed in the same period as chronic or principal care management, because CMS sees care management as work done between visits and G2211 as work done during them.
The code was valued by crosswalk to CPT 90785, the interactive complexity add-on used in psychotherapy, at a work RVU of 0.33 (CY 2027 PFS final rule). Our guide to how mental health insurance billing works covers 90785 itself.
When G2211 applies and when it doesn’t
G2211 applies when the billing practitioner has taken responsibility, or plans to take responsibility, for the patient’s ongoing care with consistency and continuity over time. It doesn’t apply when the relationship is “discrete, routine, or time-limited.” No specific diagnosis is required, and CMS gives no minimum number of visits (CMS G2211 FAQs, Q1, Q8 and Q9).
| Likely appropriate (CMS examples) | Not appropriate (CMS examples) |
|---|---|
| A primary care practitioner treating any problem, even sinus congestion, for a patient whose care they direct | Removing a mole, or referring a patient for mole removal |
| An infectious disease physician providing ongoing HIV care | Treating a simple virus |
| A practitioner who is part of ongoing care for sickle cell disease | Counseling for seasonal allergies |
| Ongoing management of a chronic condition such as hypertension, the most common condition billed with G2211 in 2024 | Initial onset of gastroesophageal reflux disease, or treating a fracture, where comorbidities are not present or not addressed |
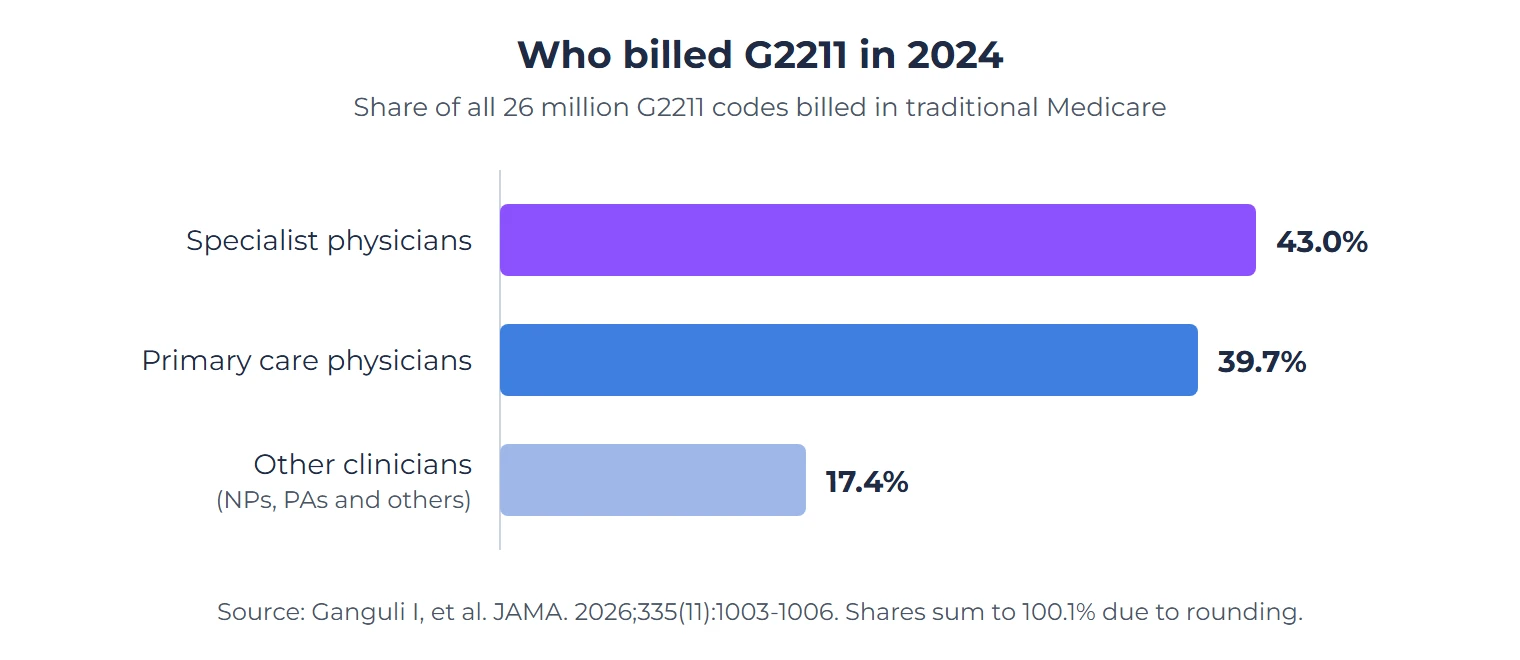
The specialist side is where most of the risk sits. Specialists billed 43.0% of all G2211 codes in 2024, more than primary care physicians at 39.7% (Ganguli et al., JAMA, 2026). The same study found that 15.2% of the first G2211-billed visits between a clinician and a patient had no prior or subsequent visit with that clinician, and that common specialist diagnoses included asymptomatic coronary artery disease, GERD and mild glaucoma. Those are the patterns a payer review would look at first.
How to bill G2211 step by step
By the end of these steps, a visit that qualifies will carry G2211 (or, from 2027, modifier B1) on a clean claim, and one that doesn’t will go out without it.
- Confirm the base code. The visit must be billed with an office or outpatient code (99202 to 99205, 99211 to 99215) or a home or residence code (99341, 99342, 99344, 99345, 99347 to 99350). G2211 is never billed on its own.
- Confirm the relationship. Ask whether this practitioner, or the practice’s care team, is the patient’s continuing focal point for care, or is managing a single serious or complex condition over time. If the visit is a one-off, skip G2211.
- Check for modifier 25. If the E/M carries modifier 25, Medicare denies G2211 unless the same-day service is an annual wellness visit, a vaccine administration or another Medicare Part B preventive service. Since January 2026 that exception also covers home or residence visits (CMS G2211 FAQs, Q6). A minor procedure on the same day, such as a joint injection, still blocks it, and the same rule applies to modifier B1 in 2027.
- Add G2211 as its own line for 2026 dates of service. G2211 is a separate claim line, with the same date of service and rendering provider as the E/M line. Point it to the diagnosis that reflects the ongoing care. For dates of service from January 1, 2027, there is no separate line: append modifier B1, or B2 for eligible ACO clinicians, to the E/M line itself.
- Check the payer. The rules above are Medicare’s. Medicare Advantage and commercial plans set their own policies on G2211 and on the new modifiers, so check each contract before adding them to non-Medicare claims.
- Tell the patient it carries cost sharing. The usual Part B deductible and coinsurance apply to G2211 (MLN Matters MM13473). Front-desk scripts should cover this, because patients notice a new line on their statement.
Modifier 25 is the rule most likely to trip up a G2211 claim, because it depends on what else happened that day rather than on the visit itself. Our modifier 24 vs 25 guide explains when modifier 25 belongs on the E/M in the first place.
What to document for G2211
CMS has not set any extra documentation requirement for G2211. The visit itself has to be reasonable and necessary, and Medicare’s reviewers “may use the medical record documentation to confirm the medical necessity of the visit and the patient care relationship.” CMS expects the diagnoses, the practitioner’s assessment and plan of care, and other codes in the claims history to serve as support (CMS G2211 FAQs, Q7).
That does not change in 2027. CMS finalized modifier B1 to be billed in the same circumstances as G2211, with a descriptor that matches G2211’s apart from technical changes. So the note should keep letting a reviewer see the relationship without opening other records. The elements below make that easier. They are good practice, not CMS requirements:
- The ongoing role. A short line such as “patient’s primary care practitioner, managing all chronic conditions” or “following for ongoing management of rheumatoid arthritis.”
- The condition being managed over time. The diagnosis pointed to on the G2211 line, or on the E/M line that carries B1, should be one the practitioner is actively managing, not a self-limited problem.
- A plan that looks forward. Follow-up interval, medication changes, monitoring or referrals coordinated by this practitioner.
- Shared decision-making. CMS describes the collaborative care behind G2211 as including patient education, expectations and responsibilities, and shared decisions about treatment goals.
Template language that pastes the same G2211 sentence into every note proves nothing. A reviewer will compare it with the claims history, and a patient seen once with no follow-up won’t support it.
How much does G2211 pay in 2026?
G2211 has a total non-facility value of 0.52 RVUs: 0.33 work, 0.17 practice expense and 0.02 malpractice. In a facility setting it is 0.43 RVUs (CMS RVU26D file). At the 2026 non-qualifying conversion factor of $33.4009 (CMS CY 2026 PFS final rule fact sheet), that is about $17.37 per visit nationally, before your locality’s geographic adjustment. The patient’s 20% Part B coinsurance on that amount is about $3.47.
The amount is small per visit and large across a panel. In 2024, Medicare paid $394 million for 26 million G2211 codes billed by 206,813 clinicians. Clinicians who used the code billed it on a median of 30.1% of their eligible visits (Ganguli et al., JAMA, 2026).
What changes in 2027: modifiers B1 and B2
In the CY 2027 Physician Fee Schedule final rule (CMS-1848-F), released November 4, 2026 and effective January 1, 2027, CMS finalized deleting G2211 and replacing it with two modifiers that go on the E/M line itself. The placeholders from the July proposal, MOD1 and MOD2, became modifiers B1 and B2 (final rule, public inspection copy):
- Modifier B1 goes on the office, outpatient or home visit line. It is billed in the same circumstances G2211 is billed now, and CMS describes it as a 16% increase to the visit.
- Modifier B2 is the ACO version, at 32%. Only clinicians participating in a Shared Savings Program ACO, or Participant Providers in a LEAD Model ACO, can use it. CMS’s fact sheet says it is voluntary and can go on visits for any patient those clinicians see, not only patients assigned or aligned to the ACO.
- The modifier 25 limit stays. CMS asked whether to allow the modifiers with 0-, 10- and 90-day global procedures and decided not to change the rule. B1 and B2 pay with modifier 25 only when the same-day service is an annual wellness visit, a vaccine administration or another Part B preventive service, including the Initial Preventive Physical Examination.
- Telehealth is allowed. The office and home E/M codes are on the Medicare telehealth list, so B1 and B2 can go on those visits when all other requirements are met.
- Other settings are out. B1 and B2 cannot be used with E/M visits in skilled nursing facilities, rural health clinics, federally qualified health centers, critical access hospitals or other places of service.
- Modifier slots. If your billing system holds only four modifiers per line, CMS points to the overflow rule in the Medicare Claims Processing Manual: modifier 99 in the fourth position and the rest in the claim’s narrative field.
CMS’s reason for the change has not moved since July. A flat add-on rewards low-level visits more than complex ones: G2211 adds 29% to the value of a 99212 (1.78 total non-facility RVUs in 2026) but only 9% to a 99215 (5.76). CMS set the modifier at 16% using a utilization-weighted average of that share, adjusted for budget neutrality.
How much will modifier B1 pay in 2027?
The short answer: at 2027 national non-facility rates, B1 adds about $6.85 to $14.72 to a 99213 and about $10.11 to $20.99 to a 99214, against a flat $17.37 per visit for G2211 in 2026. The range is wide because CMS’s own documents disagree on what the 16% applies to.
What the 16% applies to is not settled on paper. CMS’s fact sheet says B1 will “increase the payment of the associated E/M code by 16%,” and the rule’s impact analysis describes it as 16% of the visit’s total RVUs. But the B1 and B2 crosswalk file CMS posted with the rule applies the 16% to work RVUs only, and its footnote says so (CMS-1848-F downloads, “Mod B1 B2 Adjusted RVUs”). CMS derived the 16% from G2211’s share of each visit’s total value, which fits the fact sheet’s reading. Your Medicare Administrative Contractor’s 2027 fee schedule is what will settle it.
These are the 2027 non-facility RVUs under each reading, from the final rule’s Addendum B and the crosswalk file:
| Visit | 2027 RVUs, visit alone | With B1 at 16% of the visit | With B1 per CMS crosswalk file |
|---|---|---|---|
| 99212 | 1.77 | 2.05 | 1.88 |
| 99213 | 2.82 | 3.27 | 3.03 |
| 99214 | 4.02 | 4.66 | 4.33 |
| 99215 | 5.62 | 6.52 | 6.07 |
In dollars, at the 2027 non-qualifying conversion factor of $32.6286, the gap looks like this:
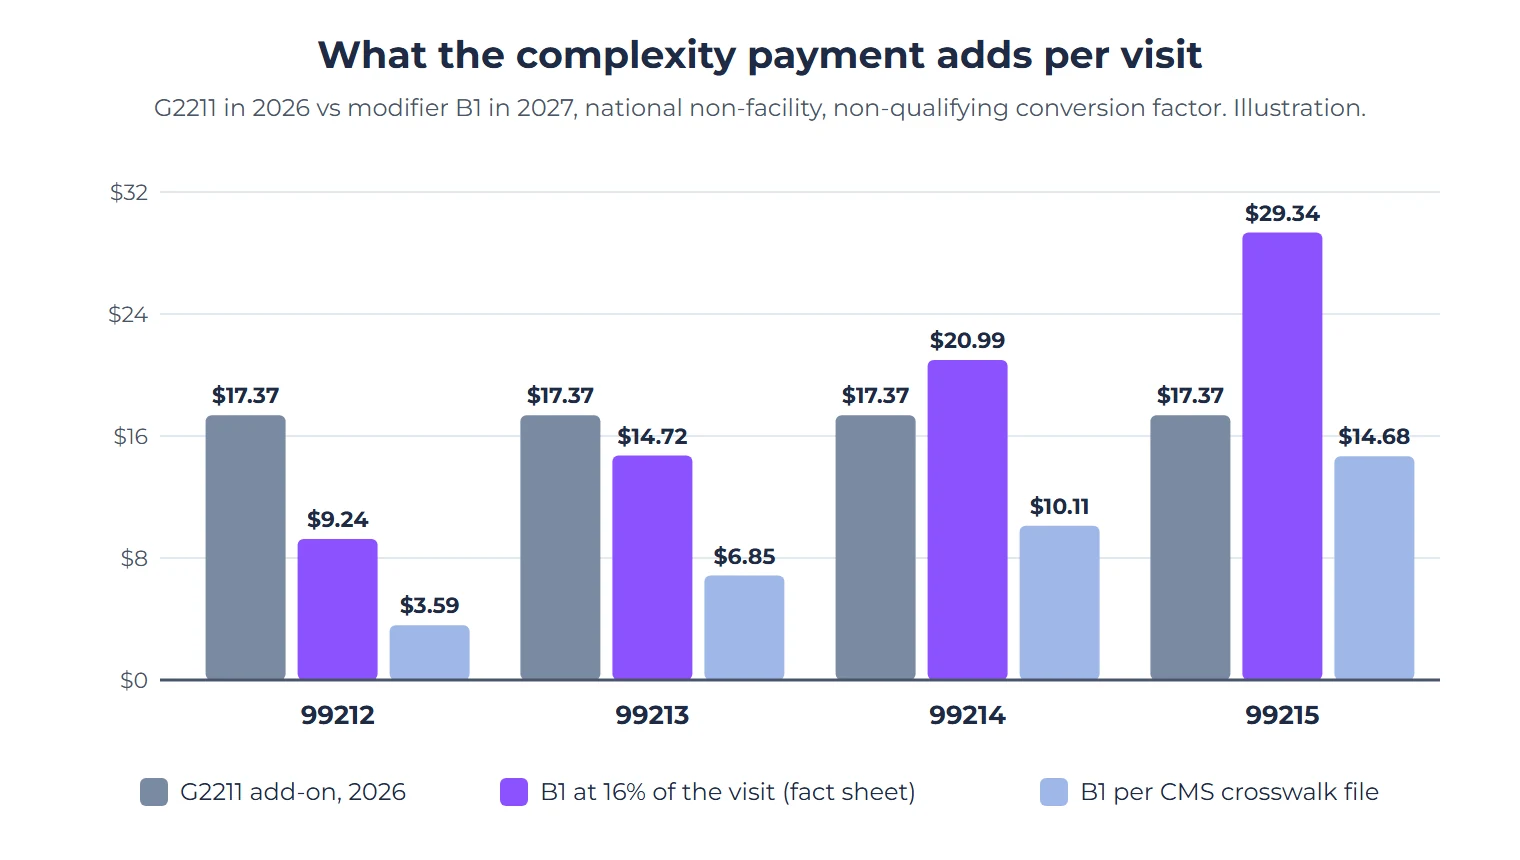
The math has a break-even point. Under the fact sheet’s reading, B1 pays more than G2211’s $17.37 only on visits worth more than about 3.33 total RVUs, which means a 99214 or 99215 but not a 99212 or 99213. Under the crosswalk file’s reading, B1 pays less than G2211 did on every established-patient office visit, and only a few high-level visits such as 99205 and 99345 come out ahead. B2 is double B1 under either reading. These are illustrations at national non-facility rates. Your locality and your contractor’s final pricing will change the real numbers.
The visit itself also pays less in 2027, because the conversion factor fell 2.31%. A 99213 drops from $95.19 to $92.01 nationally before the complexity payment is added (CMS-1848-F downloads, “Impact of Payment for Selected Procedures”). So a practice that bills G2211 mostly on short follow-ups should expect less from the complexity payment in 2027 under either reading. A practice that bills it mostly on level 4 and 5 visits comes out about even or ahead only under the fact sheet’s reading.
How to prepare for January 1, 2027
Nothing changes for 2026 dates of service, so keep billing G2211 under the current rules until December 31. These steps get the switch right:
- Measure your current G2211 rate. For each practitioner, count eligible visits and how many carried G2211. A rate near zero usually means missed revenue; a rate near 100% across every patient usually means the relationship test isn’t being applied. The same test carries over to B1.
- Find the modifier 25 denials. Pull 2026 G2211 denials and check whether the same-day service was preventive (payable) or a procedure (not payable). Fix the rule in your claim scrubber, not by hand, because B1 follows it too.
- Check the visit-level mix. Group your G2211 visits by E/M level and price them with the table above, under both readings, to see what the switch does to your revenue.
- Confirm ACO status. If your TIN participates in a Shared Savings Program ACO, or has joined the LEAD Model for 2027, decide whether your clinicians will use B2.
- Make the system change. Stop G2211 for dates of service from January 1, 2027, and add B1 (and B2 where it applies) to the E/M lines in your charge master, EHR order sets, superbills and scrubber edits. Keep G2211 available for 2026 visits billed late, and set up the modifier 99 overflow if your system holds four modifiers.
- Ask your other payers. The rule sets traditional Medicare payment, and CMS said it “does not directly govern” how Medicare Advantage plans pay contracted providers. Ask each plan in writing whether it will accept B1 and B2 in 2027, how it will price them, and whether it will still accept G2211.
- Watch for your contractor’s 2027 fee schedule. Load B1 rates only once your MAC publishes them, or once CMS clarifies which calculation applies.
How Summit handles G2211
Our coders check G2211 on eligible Medicare visits against four things: the base code, the relationship, the modifier 25 rule and the note. From January 2027 the same checks apply to modifier B1, and to B2 for practices in a Medicare ACO. When a practice’s rate looks off in either direction, we flag it at the provider level so it can be fixed before a payer asks. It’s part of our medical coding services, and our family practice billing team applies it alongside care management and annual wellness visits. If G2211 denials are already piling up, our denial management team works them back.
Want to know how your E/M billing will hold up when G2211 becomes modifier B1?
Summit Billing Solutions will look at your clean-claim rate, denial rate, aging A/R and the payers costing you the most in a free account review.
Frequently Asked Questions About G2211
1. Can nurse practitioners and physician assistants bill G2211?
Yes. Any practitioner who can bill Medicare for office or outpatient E/M visits, or home or residence E/M visits, can report G2211, and CMS does not limit it by specialty. In 2024, nurse practitioners, physician assistants and other non-physician clinicians billed 17.4% of all G2211 codes. The same applies to modifier B1 from 2027.
2. Can specialists bill G2211?
Yes, when they are part of ongoing care for a single, serious condition or a complex condition, such as an infectious disease physician managing HIV. They shouldn’t bill it when the relationship is discrete, routine or time-limited, such as a one-time consultation or a mole removal. Specialists billed 43.0% of all G2211 codes in 2024.
3. Does G2211 need a specific diagnosis code?
No. CMS does not require a particular diagnosis for G2211. The diagnosis on the claim should reflect the condition the practitioner is managing over time, and the assessment and plan should show that ongoing role.
4. Can G2211 be billed with a home visit?
Yes, since January 1, 2026. Medicare now pays G2211 with home or residence E/M codes 99341, 99342, 99344, 99345 and 99347 to 99350. It still can’t be billed with hospital inpatient, emergency department or nursing facility E/M codes. From 2027, modifier B1 can go on the same home visit codes.
5. What is the RVU value of G2211?
In 2026, G2211 is worth 0.52 total RVUs in a non-facility setting (0.33 work, 0.17 practice expense and 0.02 malpractice) and 0.43 in a facility setting, about $17.37 nationally. In 2027 it has no RVUs of its own, because modifier B1 raises the value of the visit it is attached to.
6. Will G2211 still exist in 2027?
No. For dates of service from January 1, 2027, CMS replaced G2211 with modifier B1, which goes on the office, outpatient or home E/M line, or modifier B2 at 32% for clinicians in a Shared Savings Program or LEAD Model ACO. The billing rules stay the same. Keep billing G2211 for 2026 dates of service.