


MCG clinical guidelines are evidence-based care guidelines that health plans, hospitals and government agencies use to judge medical necessity, the right level of care and the expected length of stay. MCG was formerly called Milliman Care Guidelines, which is why many people still call its criteria the Milliman criteria. Hearst has owned the company since 2012 (MCG history).
MCG says its guidelines are licensed by a vast majority of health plans and used in more than 3,200 hospitals (MCG, March 2026). So when a payer reviews a prior authorization request, an inpatient admission or a continued stay, MCG criteria are often behind the decision. For a practice, that matters most when a service is denied for medical necessity.
This guide explains what MCG criteria are, who owns them and how payers use them. It also covers the Medicare Advantage rules that limit them and how to respond when a denial cites them.
Key Takeaways
- MCG clinical guidelines, formerly Milliman Care Guidelines, are licensed, evidence-based criteria for medical necessity, level of care and length of stay. They support clinical judgment rather than replace it.
- MCG criteria are not coverage rules. The patient’s benefits, the payer’s policies and, for Medicare Advantage, Traditional Medicare coverage rules come first.
- Medicare Advantage plans must follow Medicare’s inpatient admission criteria, including the two-midnight benchmark. They can use their own internal criteria only where Medicare’s are not fully established.
- In 2024, Medicare Advantage insurers denied 7.7% of 52.8 million prior authorization requests. Only 11.5% of denials were appealed, and 80.7% of appeals were partly or fully favorable (KFF, January 2026).
- Employer plans covered by ERISA must give you the guideline behind a denial free of charge on request, which makes an MCG-based denial easier to appeal.
What Are MCG Clinical Guidelines?
MCG clinical guidelines are structured, evidence-based guidance on how and where care should be delivered. Each year, MCG’s clinical editors analyze and classify peer-reviewed research to update them, and the guidelines hold URAC accreditation for clinical review criteria (MCG care guidelines).
MCG sells versions for both payers and providers, covering these care settings (same source):
- Inpatient care
- Ambulatory care
- Behavioral health care
- Medicare compliance
- Post-acute care, including recovery facility and home care
- Chronic care
- Transitions of care
For hospital stays, the inpatient care guidelines cover three things. They define clinical indications for an admission or procedure, give rapid-review guidance on inpatient versus observation status, and set a goal length of stay (MCG inpatient care). Reviewers apply them in prior authorization, concurrent (continued-stay) review, discharge planning and retrospective claim review.
The guidelines don’t replace the treating physician’s judgment, the patient’s circumstances, the plan’s benefits or government coverage rules. That distinction drives most of what follows.
What Does MCG Stand For?
MCG is the name of the company formerly known as Milliman Care Guidelines. The guidelines began in 1988, when actuaries at the consulting firm Milliman worked with physicians to write the first evidence-based care guidelines. In November 2012, Hearst Corporation bought Milliman Care Guidelines, LLC, and the organization became MCG Health (MCG history).
That history explains the search terms people still use. Milliman criteria, Milliman Care Guidelines, Milliman Clinical Guidelines and Milliman MCG all point to what is now MCG.
Who Owns MCG Guidelines?
Hearst owns MCG Health. Since January 2014, MCG has been part of Hearst Health, the brand Hearst created for its healthcare information businesses (MCG history).
MCG isn’t owned by Medicare, Medicaid, a health system or an insurer. That matters because the same guidelines are used on both sides of a review: by the health plan deciding a request and by the hospital preparing for it.
What Are MCG Criteria (Milliman Criteria)?
MCG criteria, still often called Milliman criteria, are the clinical indications inside a licensed MCG guideline. They describe the findings that support a service, an admission or a level of care, and they differ by condition, procedure and setting.
A reviewer applying them typically looks for:
- The diagnosis, the symptoms and how severe they are
- Vital signs, lab results and imaging findings
- Treatments already tried and how the patient responded
- Comorbidities and risk factors
- The interventions and monitoring the patient needs
- Whether a lower level of care would be safe
- Progress toward discharge
The criteria aren’t a checklist to copy from one patient to the next. Two patients with the same diagnosis code can need different levels of care, and a reviewer can only weigh what the record shows. If the symptoms, failed treatments, risk factors or the physician’s reasoning aren’t documented, the record may fall short of the criteria even when the care was right.
MCG Criteria for Inpatient Admission and the Two-Midnight Rule
For Medicare Advantage patients, MCG criteria don’t decide an inpatient admission on their own. Since January 1, 2024, Medicare Advantage plans have had to follow Medicare’s inpatient admission criteria at 42 CFR 412.3. Based on complex medical factors documented in the record, a plan must cover an inpatient admission when (CMS FAQ memo, February 6, 2024):
- the admitting physician expects the patient to need hospital care that crosses two midnights (the two-midnight benchmark)
- the physician doesn’t expect two midnights but documents why inpatient care is still necessary (the case-by-case exception)
- the admission is for a surgery on Medicare’s inpatient-only list
The two-midnight presumption is different. It’s a review instruction for Medicare’s post-payment auditors, and it doesn’t apply to Medicare Advantage. Plans can still review admissions through prior authorization, concurrent review or claim review, as long as they apply Medicare’s criteria to the individual patient (same source).
In practice, MCG inpatient guidance still helps hospitals and plans organize the clinical picture. For Medicare Advantage, though, the admitting physician’s documented expectation and reasoning carry the decision. Commercial and Medicaid plans may apply MCG admission criteria more directly, so check each plan’s policy.
Are MCG Criteria the Same as Insurance Coverage Rules?
No. MCG guidelines are clinical decision support. Whether a service is covered depends on:
- the patient’s benefit plan and the payer’s medical policies
- the provider’s contract
- prior authorization requirements
- Medicare National and Local Coverage Determinations
- federal and state law
Medicare Advantage shows how the layers fit. Plans must follow National Coverage Determinations, Local Coverage Determinations and the general coverage rules of Traditional Medicare. Only where Medicare’s criteria aren’t fully established can a plan use internal criteria. Those criteria must be based on widely used treatment guidelines or clinical literature and made publicly available to CMS, enrollees and providers (CMS fact sheet on CMS-4201-F, April 2023). CMS added in February 2024 that simply referencing third-party criteria, without describing and citing the underlying evidence, doesn’t meet that standard (CMS FAQ memo).
Employer plans have their own transparency rule. An ERISA group health plan may rely on an internal rule, guideline or protocol to deny a claim. If it does, the denial notice must include it or say a copy will be provided free of charge on request. For medical necessity denials, the plan must also explain the clinical judgment behind the decision or offer that explanation free on request (29 CFR 2560.503-1).
So before you respond to any denial, identify which rules apply to that patient, payer, service and date of service.
How Are MCG Clinical Guidelines Used for Prior Authorization?
Prior authorization is where most practices meet MCG. A typical request runs like this:
- Staff confirm the patient’s coverage and whether the service needs authorization.
- Clinical documentation is gathered and sent with the request.
- The payer’s reviewer compares the record with its coverage policy and, where the payer licenses them, MCG criteria.
- The payer approves the request, denies it or asks for more information.
- The authorization number, dates and approved units are tracked through to the claim.
On the payer side, MCG’s CareWebQI platform gives health plan staff interactive access to the guidelines for utilization management reviews (MCG CareWebQI).
The volume is large. KFF found that Medicare Advantage insurers received 52.8 million prior authorization requests in 2024 and fully or partially denied 4.1 million of them, or 7.7%. Only 11.5% of the denials were appealed, but 80.7% of appeals were partly or fully favorable (KFF, January 28, 2026, based on CMS Part C reporting data).
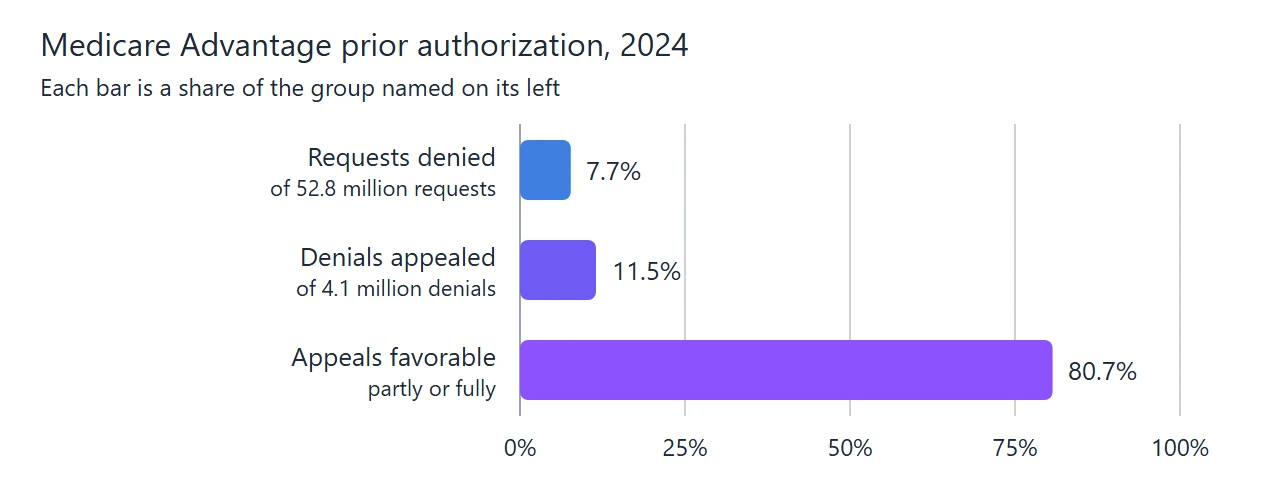
Most denials are never challenged, yet most challenges succeed. That is the strongest argument for appealing medical necessity denials that look wrong.
The rules on timing and transparency are also tightening. The CMS Interoperability and Prior Authorization Final Rule (CMS-0057-F) covers Medicare Advantage plans and Medicaid and CHIP programs, including their managed care plans. It also covers Qualified Health Plan issuers on the federal exchanges. Its main dates are (CMS fact sheet on CMS-0057-F, January 2024):
- January 1, 2026: decisions within 72 hours for expedited requests and 7 calendar days for standard requests (the exchange plans are exempt from these deadlines)
- 2026: a specific reason for every denied prior authorization request
- March 31, 2026: the first annual prior authorization metrics posted on payer websites
- January 1, 2027: prior authorization APIs in place
MCG says its MCG Path product is the only one that makes MCG care guidelines available through HL7 FHIR-based APIs, and that it supports compliance with CMS-0057-F (MCG Path).
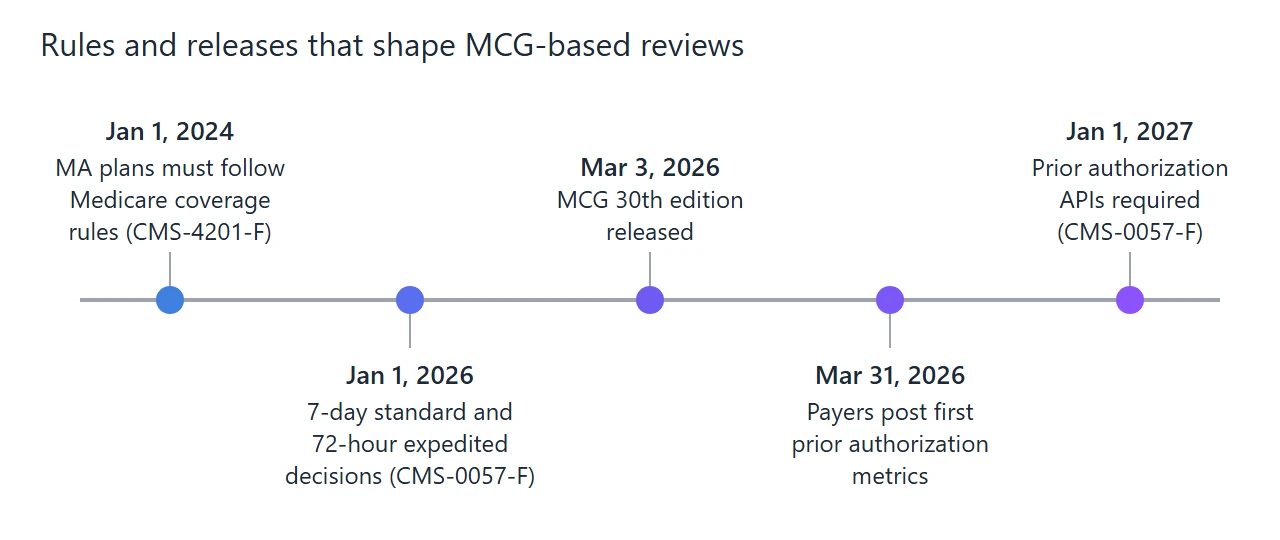
Automation won’t fix a thin record, though. An API can only send what was documented.
Why MCG Clinical Guidelines Matter for Medical Billing
A practice can deliver the right care and still lose the payment when documentation, authorization and billing don’t line up. MCG touches four parts of the revenue cycle:
- Medical necessity documentation. Reviewers look for the findings the criteria describe. Notes that state the symptoms, severity, failed treatments and the physician’s reasoning answer those questions before they’re asked.
- Prior authorization. A missing or mismatched authorization is one of the most avoidable denials. Track authorization numbers, approved services and units, and start and end dates. Our prior authorization services handle this tracking for practices.
- Denials and appeals. Clinical denials take more work than coding corrections because they turn on records and criteria, not a missing modifier. A denial management process should separate medical necessity denials from technical ones before deciding how to respond.
- Handoffs. Clinicians, authorization staff, coders and billers each see part of the same episode. Weak handoffs between them create delays that look like payer problems.
How to Appeal a Denial Based on MCG Criteria
When a denial cites MCG or medical necessity, a targeted appeal works better than resubmitting the same records:
- Get the criteria. Ask the plan for the specific guideline and the clinical rationale. ERISA plans must provide both free of charge on request, and Medicare Advantage plans must publish any internal criteria they use.
- Read the denial reason. Under CMS-0057-F, Medicare Advantage, Medicaid, CHIP and exchange plans must give a specific reason for prior authorization denials from 2026, so the gap should be named.
- Answer each indication. Show where the record documents each criterion the reviewer said was missing, such as vital signs, test results, failed treatments or risk factors.
- Bring in the physician. Request a peer-to-peer discussion where the plan offers one, and have the treating physician explain the clinical reasoning.
- Check the rule order. For Medicare Advantage, cite Traditional Medicare criteria, such as the inpatient admission rules, when the plan relied on stricter internal criteria.
- Track the outcome. Repeated denials for the same service point to a documentation or workflow gap that should be fixed upstream.
KFF’s data shows the effort pays off: 80.7% of Medicare Advantage prior authorization appeals were partly or fully favorable in 2024. A medical billing audit that compares denied claims with the notes shows which denials are worth appealing.
What Are the Benefits of MCG Clinical Guidelines in Hospital Management?
For hospitals, MCG’s main value is consistency. Evidence-based guidelines give utilization review teams a shared framework while leaving room for clinical judgment:
- Consistent utilization review. Two reviewers looking at similar cases start from the same evidence.
- Level-of-care decisions. The rapid-review guidance helps decide between inpatient and observation status.
- Earlier documentation fixes. Concurrent review can surface gaps while the patient is still in the hospital, when the record can still be clarified.
- Length-of-stay management. The goal length of stay gives case managers a benchmark for spotting barriers to discharge.
- Admission documentation support. MCG’s Indicia for Admission Documentation uses its Synapse reasoning engine to read the medical record and suggest the guidelines that fit the patient (MCG).
What Are the Limitations of MCG Clinical Guidelines?
MCG guidelines are useful, but they don’t settle every coverage question:
- They complement judgment rather than replace it. Individual patients can be more complex than any guideline.
- Meeting the criteria doesn’t guarantee payment. Eligibility, coding, authorization, contract terms, timely filing and coordination of benefits still apply.
- Missing one criterion doesn’t settle the case. Physician review and added documentation can change the outcome.
- Editions change. MCG updates its guidelines every year, so ask which edition a review relied on.
- Payers differ. Plans license different products and configure them differently, and Medicare Advantage plans are bound by Medicare’s own criteria.
Where Can You Access MCG Clinical Guidelines?
The full MCG criteria are licensed content, not a free public database. Organizations get access through MCG’s products:
| Platform | Main users | What it does |
|---|---|---|
| MCG CareWebQI | Health plans, payers and TPAs | Gives reviewers MCG criteria for utilization management and medical necessity review |
| MCG Indicia | Hospitals and providers | Supports utilization review and admission documentation inside the hospital’s workflow |
| MCG Path | Payers and their provider partners | Delivers MCG care guidelines through FHIR-based prior authorization APIs |
| MCG Synapse | Payers and providers | Uses AI reasoning to match a patient’s record with relevant guideline indications |
Be careful with websites that claim to reproduce the full MCG criteria. Current criteria come through licensed access. If you’re a provider facing a denial, though, you don’t need a license to see the criterion used against you: ask the plan for it, as described above.
Where Can Healthcare Professionals Learn How to Apply MCG Guidelines?
MCG trains its clients through an online Learning Management System, monthly 60- to 90-minute eScholar webinars, customized web or onsite training, and a one-hour Physician Leader Series. MCG certification is available to staff who use the guidelines, including trainers, managers, preceptors and super-users. To register for training, your organization must license the related MCG content or software (MCG education and training).
These programs suit utilization review nurses, physician advisors, case managers and medical directors who apply the guidelines every day.
How Do MCG Clinical Guidelines Integrate With Electronic Health Records?
Utilization review increasingly happens inside the systems clinicians already use. MCG’s Indicia for Admission Documentation analyzes the patient’s medical record with its Synapse reasoning engine and surfaces the guidelines that fit (MCG). On the payer side, CareWebQI Synapse extracts relevant clinical information from submitted documentation (MCG, March 2026), and MCG Path exchanges guideline information through FHIR APIs.
The goal is less re-keying and faster exchange between providers and payers. The limit is the same as with any automation: the tools can only find what the record contains.
MCG vs InterQual and Other Clinical Decision Support
MCG’s best-known competitor is InterQual, which Optum describes as an evidence-based clinical decision support solution for payers, providers and government agencies (Optum InterQual). Searches for “Milliman and InterQual criteria” usually compare these two. Both are licensed criteria sets for medical necessity and level-of-care review, and which one applies depends on what the payer or hospital licenses.
| Type of decision support | Main strength | Common use |
|---|---|---|
| MCG | Evidence-based care guidelines with payer, provider and authorization technology | Admission review, prior authorization, care management |
| InterQual | Evidence-based medical necessity and level-of-care criteria | Payer and provider utilization management |
| Medicare NCDs and LCDs | Official Medicare coverage requirements | Medicare and Medicare Advantage coverage decisions |
| Specialty society guidelines | Specialty-specific clinical expertise | Diagnosis and treatment recommendations |
| Internal payer policies | A payer’s own coverage rules | Authorization and medical necessity review |
No single system is right for every decision. A Medicare coverage question may call for the applicable NCD or LCD, while a hospital utilization review team may use MCG or InterQual alongside physician review and payer policies.
What Is the Latest Version of MCG Clinical Guidelines?
The latest major release is the 30th edition of the MCG care guidelines, announced on March 3, 2026. MCG says it adds new or expanded guidance on (MCG, March 2026):
- Transcatheter mitral valve repair
- Gene and cellular therapies
- Specialty medications
- Orthopedic procedures
- Behavioral health
- Inpatient cardiac rehabilitation
- Home and chronic care
- Transitions of care, aligned with the CMS TEAM bundled payment model
The 30th edition also adds structured content meant to support AI reasoning. MCG estimates that CareWebQI Synapse cuts medical necessity review time by 70% to 80%. That is the company’s own estimate, and results depend on the organization and workflow.
How Providers Can Prepare for MCG-Based Reviews
Your clinicians don’t need to become MCG experts. Your workflow needs to put the right clinical information in front of reviewers:
- Check payer requirements before treatment. Confirm whether authorization is required and which policy applies. An eligibility verification step catches plan changes before the visit.
- Document the full clinical picture. Record symptoms, severity, test results, failed conservative treatments, comorbidities and the physician’s reasoning where they apply.
- Track authorizations. Keep authorization numbers, dates, services, units, expiration dates and payer messages in one place.
- Review medical necessity denials one by one. Decide whether the problem is documentation, criteria, authorization, coding or coverage.
- Connect clinical and billing teams. Utilization review, authorization, coding, billing and denial staff should share what they learn.
- Watch for changes. MCG editions, Medicare rules and payer policies all change over time.
- Analyze denial trends. Repeated medical necessity denials for one service usually point to a fixable workflow problem.
Where Summit Billing Solutions Fits
Summit Billing Solutions works on the practice side of these reviews. We verify eligibility and authorization requirements, submit and track prior authorizations, and work medical necessity denials and appeals for practices in all 50 states.
Want to know which medical necessity denials are worth appealing?
Our free account review looks at your denials, aging A/R and top denying payers, whether or not you go further with us. You can also contact our team with a prior authorization question.
How We Researched This Guide
We checked every fact in this guide against its source on October 2, 2026. For MCG’s history, products, training and 30th edition, we used MCG’s own pages. For the rules, we used CMS fact sheets, a February 2024 CMS memo on Medicare Advantage coverage criteria and the federal ERISA claims regulation. The prior authorization figures come from KFF’s analysis of CMS data. MCG criteria themselves are licensed, so this guide describes how they are used rather than quoting them. Payer policies vary, so confirm the details with each plan.
Frequently Asked Questions About MCG Clinical Guidelines
1. What are MCG clinical guidelines?
MCG clinical guidelines are evidence-based care guidelines from MCG Health, formerly Milliman Care Guidelines. Health plans, hospitals and government agencies use them to judge medical necessity, level of care and length of stay. They support clinical judgment rather than replace it.
2. What are Milliman Clinical Guidelines?
Milliman Clinical Guidelines, or Milliman Care Guidelines, is the former name of the MCG guidelines. Milliman actuaries and physicians wrote the first ones in 1988. Hearst bought Milliman Care Guidelines in 2012, and the organization became MCG Health, so “Milliman criteria” today means MCG criteria.
3. Who owns MCG guidelines?
Hearst owns MCG Health, which has been part of Hearst Health since 2014. MCG isn’t owned by Medicare, Medicaid, a health system or an insurer.
4. What are the MCG criteria?
MCG criteria are the clinical indications in a licensed MCG guideline that support a service, admission or level of care. They include findings such as symptoms, severity, test results, prior treatments and risk factors, and they vary by condition, procedure and setting.
5. Where can I access MCG clinical guidelines?
The full guidelines are available only through a license from MCG, through products such as CareWebQI and Indicia. A provider facing a denial can ask the plan for the specific criterion used, and ERISA plans must provide it free of charge on request.
6. What is the difference between MCG and InterQual?
Both are licensed, evidence-based criteria sets for medical necessity and level-of-care review. MCG is owned by Hearst, and InterQual is offered by Optum. Which one applies depends on what the payer or hospital licenses, and neither overrides Medicare coverage rules.
7. Do Medicare Advantage plans use MCG criteria?
They can, within limits. Medicare Advantage plans must follow Traditional Medicare coverage rules, including the inpatient admission criteria. They can use internal criteria only where Medicare’s are not fully established, and those criteria and their evidence must be public.
The Bottom Line
MCG criteria shape many prior authorization and admission decisions, but they sit below the rules that actually decide coverage:
- Treat MCG, or Milliman, criteria as the reviewer’s checklist, not the coverage rule.
- For Medicare Advantage, start with Medicare’s own criteria, including the two-midnight benchmark.
- Document the findings reviewers look for, and track every authorization to the claim.
- Ask for the guideline behind any medical necessity denial, then answer it point by point.
- Appeal denials that look wrong. In Medicare Advantage, most appeals succeed.
External References
- MCG Health history
- MCG care guidelines
- MCG Inpatient Care guidelines
- MCG CareWebQI
- 30th Edition of MCG Care Guidelines, March 3, 2026
- MCG education and training
- MCG Path
- CMS fact sheet: 2024 Medicare Advantage and Part D Final Rule (CMS-4201-F)
- CMS memo: FAQs on coverage criteria and utilization management in CMS-4201-F, February 6, 2024
- CMS fact sheet: Interoperability and Prior Authorization Final Rule (CMS-0057-F)
- KFF: Medicare Advantage insurers made nearly 53 million prior authorization determinations in 2024
- 29 CFR 2560.503-1, ERISA claims procedure
- Optum InterQual