

Ophthalmology billing for solo and group practices: medical and routine vision visits, diagnostic testing, cataract and other surgery with their global periods, and intravitreal injections with high-cost Part B drugs, worked inside the software you already use by a US-based team.
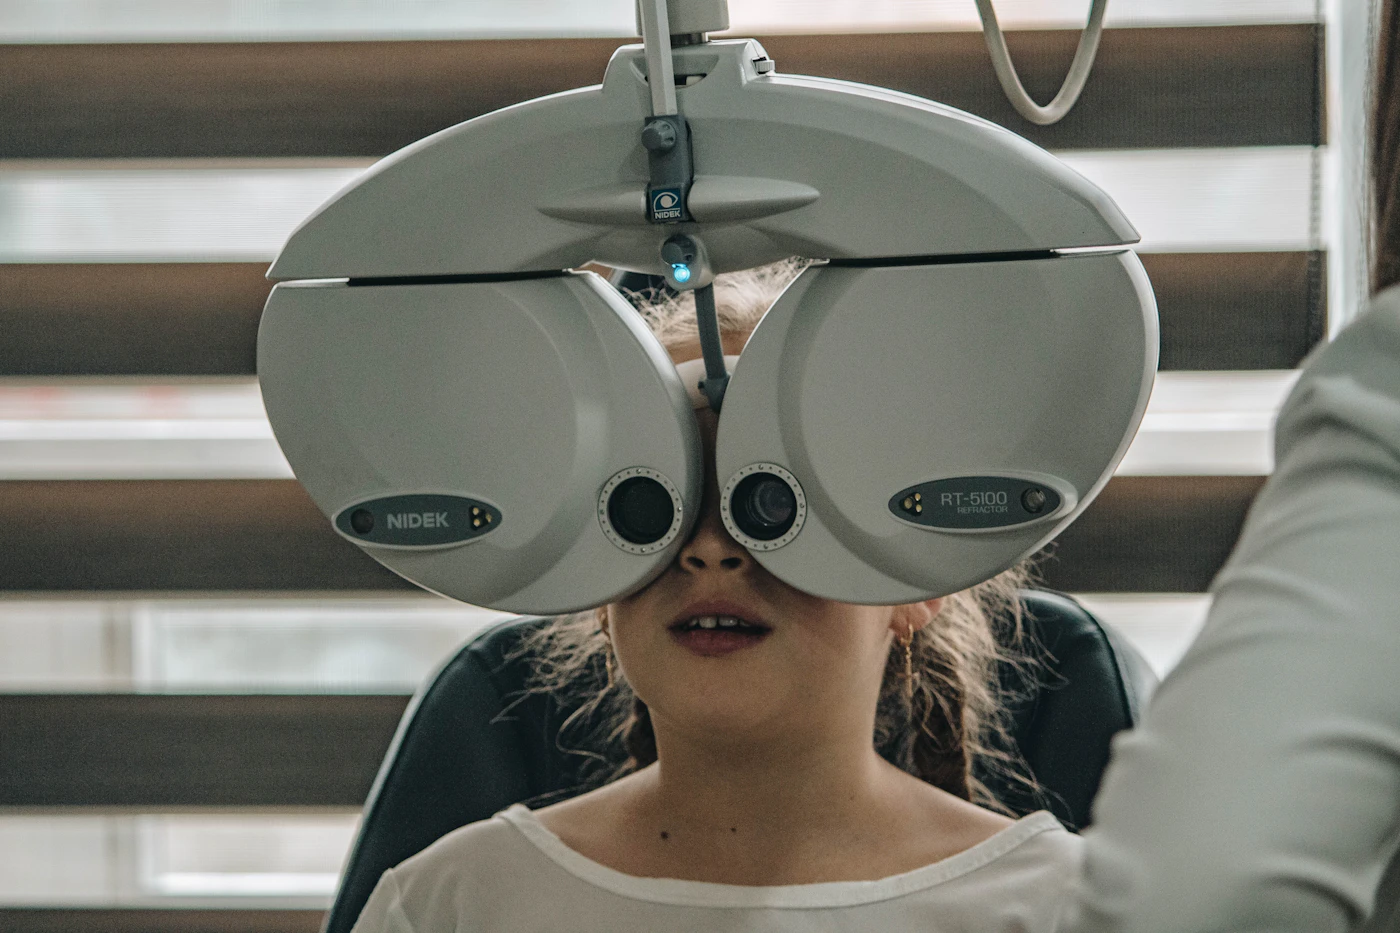

Ophthalmology billing services turn every exam, test, surgery and injection into a paid claim. Medical and vision coverage are checked before the visit, each service is coded to the eye and the diagnosis the note documents, drugs are billed by unit with their waste reported, and every payment, denial and patient balance is followed until it is resolved.
$6.2B
paid by Medicare fee-for-service for ophthalmic drugs under Part B in 2024, the third-largest drug class
31.2%
of improper Medicare payments to ophthalmology in CMS’s 2025 review were incorrect coding; most of the rest, 67.7%, were insufficient documentation
Ophthalmology bills three businesses under one roof. Routine eye exams and refractions go to vision plans or the patient, medical eye care goes to health insurance, and surgery and injections bring global periods, laterality and some of the most expensive drugs Medicare pays for. The same patient can touch all three in a year.
One drug claim can be worth more than a day of exams. That is why we check every injection claim, the drug, the units, the eye and the waste, before it goes out, not after it is denied.
Most ophthalmology practices bill vision plans, medical insurance and surgical or drug claims in the same week, often for the same patient. Each one pays differently and fails in its own way. Here is where each breaks, and what we do about it.
Pays forVision plans pay routine exams and refractions; medical plans pay exams and tests for a medical diagnosis. Medicare does not pay for refractions.
Where it breaks
What we do
Pays forA global fee for cataract and other eye surgery that covers related care for 90 days, split when another provider handles the post-op visits.
Where it breaks
What we do
Pays forThe intravitreal injection procedure, plus the drug itself billed in units, often thousands of dollars per dose.
Where it breaks
What we do
An intravitreal injection is billed as two parts: the procedure (67028) for the eye treated, and the drug, billed in units of its HCPCS code. The units have to match the dose given and the code’s billing unit, and the eye has to match the diagnosis and the note.
For single-dose containers billed to Medicare, CMS has required since July 2023 either the JZ modifier, stating nothing was discarded, or the JW modifier on a separate line for the discarded amount. Claims without them can be returned unpaid. Many Medicare Advantage and commercial plans also require prior authorization or step therapy before an anti-VEGF drug is covered.
What we do: before an injection claim goes out, we check the drug, units, NDC, eye and waste modifier against the chart. If anything does not match, we tell you the same day, rather than send a claim worth thousands that will be returned or denied.

These are the codes behind most ophthalmology claims, and what payers look for on each one. Medicare’s rules are marked; vision plans and commercial payers have their own, and we check each one.
| Code | What it covers | What payers look for |
|---|---|---|
| 9200292004 | Eye exam, new patient, intermediate and comprehensive | Medical eye exam codes, used instead of office visit codes when the documentation fits their definition. See our optometry revenue cycle guide. |
| 9201292014 | Eye exam, established patient, intermediate and comprehensive | The level matches the exam documented; some payers limit how often 92014 is paid. |
| 99202 to 99215 | Office visits (E/M) | An alternative to the eye codes, chosen by decision making or time. |
| 92015 | Refraction | Collected from the patient or billed to the vision plan.MedicareNot covered. |
| 92134 | OCT imaging of the retina | A diagnosis that supports the test, and an interpretation and report in the record. |
| 92133 | OCT imaging of the optic nerve | Used for glaucoma, with the interpretation and report documented. |
| 92083 | Visual field exam, extended | A covered diagnosis and the payer's frequency limit. |
| 6698466982 | Cataract surgery with lens implant, standard and complex | A 90-day global period. Complex only when the note documents what made it complex. |
| 66821 | YAG laser capsulotomy | Its own 90-day global period, separate from the cataract surgery's. |
| 67028 | Intravitreal injection | Per eye, with the drug billed separately in units. |
| J0178J2778 | Aflibercept and ranibizumab, anti-VEGF drugs | Units per the code's billing unit.MedicareJZ or JW on single-dose containers. |
Required on eye procedures and many tests, so a claim for each eye is paid once, and only once.
Splits a global surgical fee when the surgeon and another provider share the care.
A procedure, such as surgery on the other eye, during the post-op period of an earlier one.
An exam that is significant and separate from a minor procedure the same day. Modifier 25 explained
Required by Medicare on single-dose drug containers: JZ when nothing was discarded, JW for the discarded amount.
Services Medicare never covers, such as refractions, sent when a secondary plan needs Medicare's denial first.
Sources: Medicare Claims Processing Manual, chapter 12 (global surgery) and chapter 17 (drugs and biologicals); CMS JW and JZ Modifier FAQs. CPT is a registered trademark of the American Medical Association; the descriptions above are summaries. Reviewed October 2026.
It is not for every practice. If your in-house team keeps drug claims clean, denials low and receivables current, keep them, and consider a periodic billing audit instead.
We look at your clean-claim rate, your denials by payer and reason, drug claims and their units, global-period billing, and your aging receivables, and tell you what we find, whether or not you go further with us.
We get access to your practice management system and clearinghouse, load your medical, vision and Medicare Advantage payer rules, list open authorizations and global periods, and agree how escalations work. Most practices are live within one to two weeks.
Visits, tests, surgeries and injections are coded and claims submitted within 24 hours. Rejections are corrected the same day, remittances posted as they arrive, drug claims checked line by line, and denials worked to their cause, all inside your system.
A report you can read in ten minutes: what was billed and collected by payer and service line, drug claims paid and pending, what was denied and why, and what is aging.
You do not change systems to work with Summit Billing Solutions. We work in the practice management and EHR systems below, and through the clearinghouse you already use. If your EHR is not shown, ask; the list grows as we onboard practices.


Your claims are worked by billers who handle eye exam codes, global periods, laterality and Part B drugs every day, not once a quarter.
You know who is working your account, and you hear from them every week. A familiar face, not a ticket queue.
If we are not earning the relationship, you can leave. That keeps us honest.
Your claims are worked in the United States, with the state-by-state payer and Medicaid knowledge that takes.
2%
Average claim rejection rate
24 hrs
Claims submitted within
28
Average days in A/R

I cannot say enough wonderful things about Summit Billing Solutions. From start to finish, the experience was seamless, professional, and incredibly well organized.

Summit Billing Solutions & Consulting is a highly organized company that provides accurate and prompt billing services.

Most billing companies charge a percentage of what they collect; some charge a flat monthly fee or a per-claim rate. For an ophthalmology practice, a percentage usually fits best: the company is paid when you are paid, so the incentive sits where it belongs.
Summit Billing Solutions charges between 3% and 9% of monthly collections. What moves the number for an ophthalmology practice is visit and injection volume, the share of drug claims, the mix of medical and vision plans, and how clean the receivables are when we take them on, which is why we quote your exact rate after the free account review, not before.
3% to 9%
of monthly collections
We bill for more than 40 specialties, for practices in all 50 states, from Salem, New Hampshire. Each one has its own codes, modifiers and payer rules.
Most billing companies charge a percentage of collections, and a few charge a flat monthly or per-claim fee. Summit Billing Solutions charges between 3% and 9% of monthly collections. For an ophthalmology practice, the rate depends on visit and injection volume, the share of drug claims, the mix of medical and vision plans, and the state of your receivables, and we quote your exact rate after the free account review.
No. Refraction (92015) is not a Medicare benefit, even when it is done during a covered medical exam. It is collected from the patient or billed to a vision plan, and it can be sent to Medicare with the GY modifier when a secondary plan needs Medicare's denial first.
Either can be correct. The eye codes (92002 to 92014) are defined around the eye exam itself, while office visit codes (99202 to 99215) are chosen by decision making or time. We code each visit with whichever set the documentation fully supports, and follow any payer that prefers one.
They report drug waste on single-dose containers billed to Medicare Part B. JZ says nothing was discarded; JW goes on a separate line for the amount discarded. CMS has required one or the other since July 2023, and claims without them can be returned unpaid.
When an optometrist handles the post-op care, the surgeon bills the surgery with modifier 54 and the optometrist bills the post-op care with modifier 55, using the same procedure code and date of surgery and the date care was transferred. Both sides need the transfer documented for the split to pay.
Yes. Many Medicare Advantage and commercial plans require authorization or step therapy before an anti-VEGF drug is covered. We request it, track the approved doses and dates, and renew before they run out, so an injection is not given without coverage.
Yes. Routine exams and refractions are billed to the patient's vision plan, and medical eye care to their health insurance, decided by the reason for the visit and the diagnosis.
We work inside the system you already use, including ModMed, NextGen, eClinicalWorks, athenahealth, AdvancedMD and Tebra, and through your existing clearinghouse, so your data stays in your system. If yours is not listed, ask; the list grows as we onboard practices.
Most practices are live within one to two weeks of signing. During onboarding we take your aging report and work the oldest recoverable claims first, so nothing ages during the handover. Balances past every deadline are reported to you with a reason before anything is written off.
A free account review looks at your clean-claim rate, your denials by payer and reason, drug claims and their units, global-period billing and your aging receivables, and tells you what we would change. No cost, no obligation, and no pressure to continue. What the review covers, step by step, is on the free account review page.
50A Northwestern Drive, Salem, NH 03079
603-207-3172
(866) 906-3116
info@summitbillingsolutions.com
Mon - Fri @ 9am - 5pm





From day one, they jumped in to clean up past billing issues, optimized our claims process, and significantly reduced our AR turnaround time. They're experts in both vision and medical billing, and I never have to worry about denials slipping through the cracks.