


Audits exist because billing errors are ordinary. CMS measures its own: the fiscal year 2025 Medicare fee-for-service improper payment rate was 6.55 percent, representing $28.83 billion, according to CMS’s Comprehensive Error Rate Testing program. Improper does not mean fraudulent; most of it is documentation that does not support the claim, or a code that does not match the record. A practice audit finds the same things on your own claims, at a sample size you can afford, before a payer’s audit letter arrives.
The federal government has said how often. HHS OIG’s compliance guidance for individual and small group physician practices recommends a baseline audit and then periodic audits “at least once each year”, and gives “five or more medical records per Federal payor” as a basic guide to sample size. Summit Billing Solutions runs audits to that pattern and, for practices whose billing we handle, treats the periodic audit as part of the service. The free account review is the light version; this page is the full one.
| Number | Audit area | What we check | What a finding means, and what is next | Related service |
|---|---|---|---|---|
| 1 | Documentation support | Does the note support what was billed: the E/M level, the procedures, the units, the time, and the diagnoses on the claim. | A claim the record does not support is the finding payers care most about. Next step: the provider hears exactly what the note needed, and future claims are reviewed before submission. | Coding review |
| 2 | Coding accuracy | Whether the ICD-10-CM, CPT and HCPCS codes and the modifiers are the right ones for what the note describes, under the code sets in force on the date of service. | Wrong codes cost money both ways: under-coding is unclaimed revenue, over-coding is overpayment exposure. Next step: a corrected-claim list for what can still be refiled, and a coding education note. | Medical coding |
| 3 | Charge capture | Services documented in the record but never billed: procedures, supplies, drugs, tests and visits that dropped between the note and the claim. | The most common finding in small practices, and invisible in any denial report. Next step: refile what is still inside the payer's filing limit, and fix the step in the workflow where charges fall out. | Charge entry |
| 4 | Compliance exposure | The risk areas the OIG names for physician practices: medical necessity, incident-to conditions, NCCI bundling and units, place of service, and billing for services not rendered as documented. | A pattern here is what turns a payer's spot check into a full audit. Next step: the pattern is documented, the workflow that produced it is changed, and identified overpayments are handled under the payer's and Medicare's rules. | HIPAA compliance checklist |
| 5 | Payment accuracy | Whether each sampled claim was paid what the contract says: underpayments, contractual adjustments posted as if correct, and denials that were never worked or appealed. | Underpayments are the finding practices least expect, because nothing was denied. Next step: a recovery list with deadlines, and posting rules that flag short payments in future. | Payment posting |
| 6 | Process controls | The steps around the claim: eligibility verified before the visit, authorizations on file, claims filed inside the limit, denials worked, write-offs approved by someone with authority. | A missing control is the root cause behind most other findings. Next step: the control is added to the daily workflow, and the next audit checks that it stayed. | Denial management |
| Compare | Waiting for the payer | Summit Billing Solutions |
|---|---|---|
| Who picks the sample | The payer, from the claims that already look wrong to its software. | You and we do, across providers, payers and service types, following the OIG's basic guide. |
| What a finding costs | Recoupment, interest, a larger sample, and sometimes a referral. | A corrected claim, a workflow change, and an overpayment returned on your own terms and timeline. |
| Under-coding | Never mentioned. Payers do not audit for money they owe you. | Reported with the same weight as over-coding, with a refile list for what is still inside the filing limit. |
| Timing | Whenever the letter arrives, with a deadline you did not choose. | On your calendar, once a year at least, and before any records request is answered. |
| What the provider learns | A results letter, months later. | A short education note per provider, tied to the exact claims and notes. |
| Afterwards | You are on the payer's list. | The next audit checks that the fix held, and the report is yours to keep. |
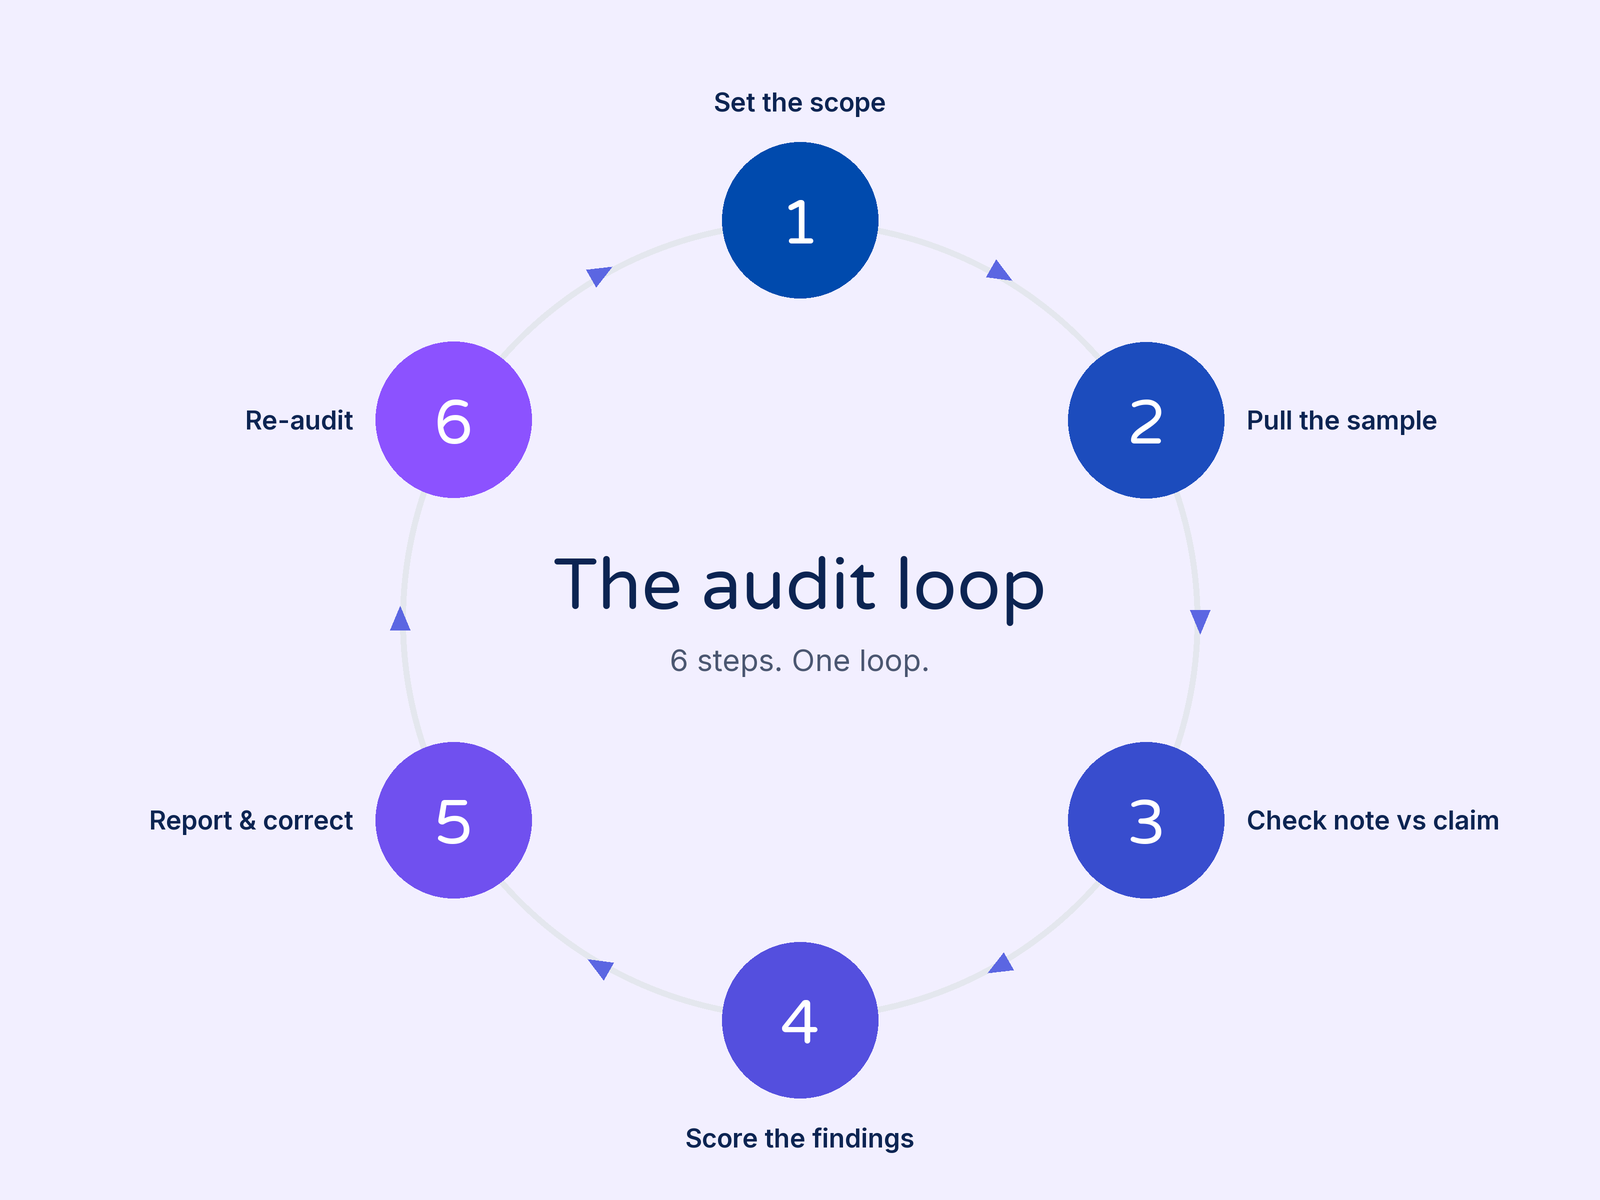
The light version first: your denials for the last 90 days, your E/M distribution by provider and your aging A/R, which tells us where a full audit should look, whether or not you go further with us.
We agree the providers, payers, date range and service types, and size the sample: at least the OIG's basic guide of five or more records per federal payer, larger where the account review pointed to a pattern. You export the claims and notes, or give us access to pull them.
Each sampled claim is checked against the note, the code sets in force on the date of service, the payer's policy, the contract rate and the remittance. Every finding is recorded with its area, its direction, its dollar value and the correction.
A written report by provider and error type with the dollar impact, a refile list, a corrections list and a short education note per provider, walked through with you. Then a date for the re-audit, so you know whether the fix held.


Your claims are worked by a team in the United States, not routed offshore.
You know who is working your account, and you hear from them every week. A familiar face, not a ticket queue.
If we are not earning the relationship, you can leave. That keeps us honest.
We are in Salem, NH, and we bill for practices nationwide, with the state-by-state payer knowledge that takes.
2%
Average claim rejection rate
24 hrs
Claims submitted within
28
Average days in A/R

I’ve been in billing for 30+ years and Summit is the best I’ve worked with. They’re knowledgeable, detailed, and persistent to get claims paid instead of writing them off. They take the burden off providers so we can focus on patients.

We billed in-house for decades, but it was time for a change. I couldn’t be happier with Summit. The transition was seamless thanks to their strong systems and clear communication. If you’re considering a switch, talk to Summit.


When Summit Billing Solutions handles your billing, a periodic audit is part of the service, inside the fee of 3% to 9% of monthly collections, because we would rather find our own errors than have a payer find them.
A standalone audit for a practice that keeps its billing in house is quoted after the free account review, by the size of the sample, the number of providers and payers, and the specialty, since those decide the hours. We do not quote a recovery figure, because an audit is a review, not a promise about what it will find. How billing companies structure their fees more generally is covered in our guide to medical billing pricing.
50A Northwestern Drive, Salem, NH 03079
603-207-3172
(866) 906-3116
info@summitbillingsolutions.com
Mon - Fri @ 9am - 5pm
Summit Billing Solutions has been one of the best decisions for my business. They’re responsive, transparent, and make billing feel organized and manageable. They truly feel like a partner, not a vendor. Highly recommend.